
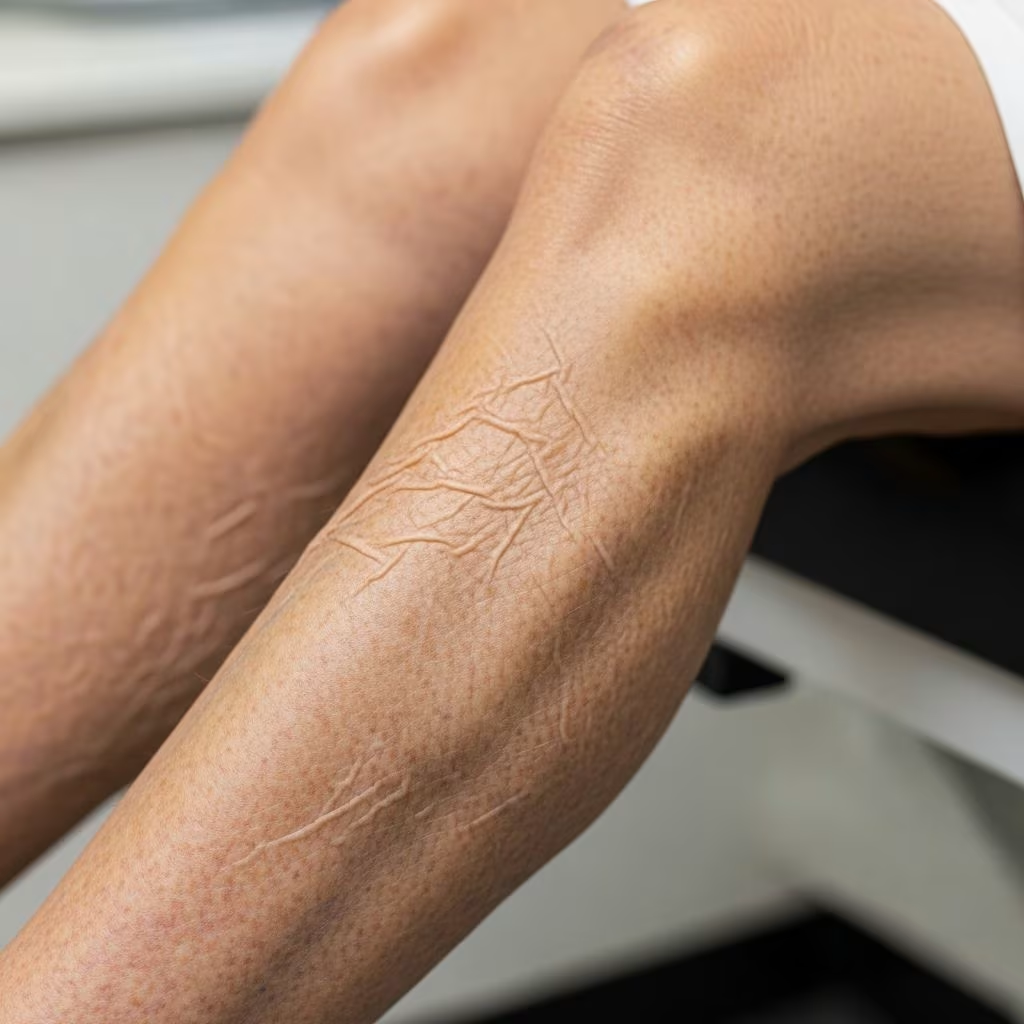
Acrodermatitis chronica atrophicans (ACA) represents the most common cutaneous manifestation of late-stage Lyme borreliosis, a tick-borne infection prevalent in Europe. This chronic dermatosis arises from persistent infection by Borrelia afzelii, leading to progressive skin changes including inflammation, fibrosis, and atrophy.
Introduction
Acrodermatitis chronica atrophicans develops months to years after an untreated tick bite transmitting Borrelia spirochetes, distinguishing it from acute Lyme rashes like erythema migrans. Primarily observed in Europe due to the endemicity of B. afzelii, ACA affects 1–10% of Lyme-infected individuals, underscoring its significance in endemic regions. If unrecognized, the condition evolves from reversible inflammatory lesions to irreversible atrophic skin damage.
Causes
ACA results from ongoing cutaneous infection by Borrelia afzelii, a spirochete transmitted via Ixodes tick bites in Europe. Less commonly, Borrelia garinii or Borrelia burgdorferi sensu stricto (European strains) are implicated. The bacteria persist in the skin, evading immune clearance and driving chronic inflammation.
- Tick exposure in endemic areas (grasslands, woodlands) precedes ACA by 6 months to 8 years.
- Untreated early Lyme manifestations, such as erythema migrans on the same limb, occur in ~20% of cases.
Demographics
ACA predominantly impacts women aged 40–70 years, though it can affect any age, including children. It is rare in the United States, where B. burgdorferi strains prevail, but common in Europe, comprising ~10% of Lyme borreliosis cases there.
Clinical Features
ACA manifests unilaterally on acral sites—extensor surfaces of hands, elbows, feet, ankles, or knees—with potential bilateral or truncal involvement. It progresses in two phases: early inflammatory and late atrophic.
Early Inflammatory Stage
Initial lesions appear as bluish-red or violet patches with doughy swelling and oedema. These may be subtle, allowing asymptomatic progression.
Late Atrophic Stage
Over months to years, inflammation yields to fibrosis, sclerosis, and atrophy, resulting in thin, wrinkled, ivory- or porcelain-coloured skin with telangiectasia. Hair loss and anhidrosis occur in atrophic areas.
- Less common features: Fibrous papules, plaques, or subcutaneous nodules; sclerotic bands restricting joint mobility (~15% of cases).
- Associated symptoms: Peripheral neuropathy (numbness, paraesthesia, allodynia in ~50%); rare tenosynovitis or dactylitis causing limb swelling.
Systemic late Lyme features may coexist: arthritis (North America), neuroborreliosis, or acrodermatitis.
Differential Diagnoses
ACA’s varied presentation mimics numerous conditions, necessitating careful exclusion.
| Category | Conditions |
|---|---|
| Atrophic lesions | Chronic venous/arterial insufficiency, cold injury, livedo reticularis, localised scleroderma, erysipelas, lymphedema, corticosteroid atrophy, ageing. |
| Nodules/lumps | Rheumatoid nodules, gout, erythema nodosum. |
Diagnosis
Diagnosis integrates clinical history (tick exposure, prior erythema migrans), examination, and laboratory confirmation. Full skin survey is essential.
- Serology: Positive IgG ELISA followed by immunoblot; elevated in late disease.
- Histopathology: Skin biopsy reveals dermal lymphocytic infiltrate, plasma cells, telangiectasia; later, epidermal atrophy and fibrosis.
- PCR: Detects Borrelia DNA in skin biopsy (higher sensitivity in early ACA).
- Culture: Rarely positive from biopsy.
Neurological symptoms warrant CSF analysis; joint involvement requires synovial fluid evaluation.
Treatment
Antibiotics eradicate infection, most effective in early inflammatory phase when skin changes reverse. Selection depends on organ involvement and severity.
| Antibiotic | Dose/Duration | Notes |
|---|---|---|
| Doxycycline | 100 mg twice daily, 21–28 days | First-line oral for skin-limited disease. |
| Amoxicillin | 500 mg three times daily, 21–28 days | Alternative for pregnancy/children. |
| Ceftriaxone | 2 g IV daily, 14–21 days | For extracutaneous involvement (neuroborreliosis). |
| Penicillin G | 20 million IU IV daily, 14–21 days | Severe cases. |
- Monitor response; extend therapy for persistent symptoms.
- Refer to neurology/rheumatology if needed.
Outcome
Early treatment resolves inflammation and prevents progression. In atrophic stages, infection clears but skin atrophy persists, with potential residual neuropathy. Untreated ACA risks secondary bacterial infections and rarely B-cell lymphoma.
Prevention
No Borrelia vaccine exists; focus on tick avoidance.
- Wear protective clothing in endemic areas.
- Use DEET repellents.
- Perform daily tick checks; remove ticks promptly with tweezers.
- Seek early evaluation for erythema migrans.
Frequently Asked Questions (FAQs)
Q: Who is at risk for acrodermatitis chronica atrophicans?
A: Primarily middle-aged/older women in Europe with untreated Lyme exposure; rare in children or US residents.
Q: Can ACA resolve without treatment?
A: No, untreated lesions progress to irreversible atrophy; antibiotics are essential.
Q: How long after a tick bite does ACA appear?
A: Months to years (6 months–8 years).
Q: Is ACA contagious?
A: No, transmitted only via infected tick bites, not person-to-person.
Q: What does ACA skin look like?
A: Early: bluish-red swollen patches; late: thin, wrinkled, ivory skin on limbs.
Q: Can antibiotics reverse late-stage skin changes?
A: Infection clears, but atrophy persists; best outcomes in early phase.
References
- Acrodermatitis Chronica Atrophicans (Lyme Disease) — MD Searchlight. 2023. https://mdsearchlight.com/wilderness-and-environmental/acrodermatitis-chronica-atrophicans-lyme-disease/
- Acrodermatitis chronica atrophicans — DermNet NZ (Dr Daniela Vanousova, Dr Amanda Oakley). 2021-10. https://dermnetnz.org/topics/acrodermatitis-chronica-atrophicans



