Anticonvulsant drugs, also known as antiseizure medications (ASMs), are essential for managing epilepsy and other neurological conditions. However, they are associated with a wide range of cutaneous adverse effects, ranging from mild rashes to severe, life-threatening reactions. These skin manifestations affect 2-16% of patients, with aromatic ASMs like carbamazepine (CBZ), phenytoin (PHT), phenobarbital (PB), and lamotrigine (LTG) being most implicated. Early recognition is critical to prevent progression to syndromes like drug reaction with eosinophilia and systemic symptoms (DRESS), Stevens-Johnson syndrome (SJS), or toxic epidermal necrolysis (TEN).
What are the cutaneous adverse effects of anticonvulsant drugs?
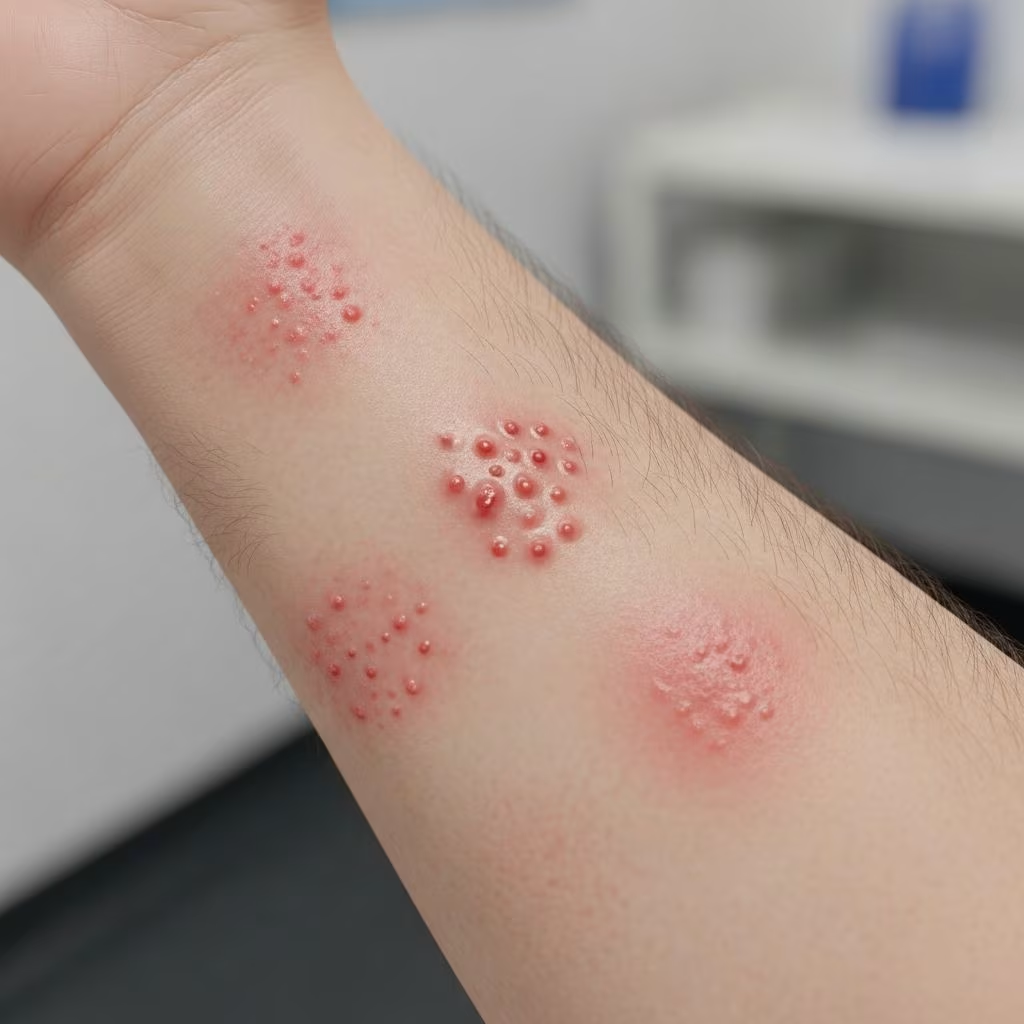
Cutaneous adverse drug reactions (cADRs) to anticonvulsants encompass benign eruptions like maculopapular rashes and urticaria, as well as severe idiosyncratic reactions including SJS/TEN and DRESS. Maculopapular eruptions, the most common, present as erythematous, pruritic macules and papules on the torso and limbs 7-14 days after initiation, resolving 1-2 weeks post-discontinuation. Urticarial reactions cause itchy, transient hives, particularly in atopics. Severe reactions involve epidermal necrosis (SJS/TEN) or systemic hypersensitivity (DRESS), with ASMs accounting for up to 53% of DRESS cases.
Who gets cutaneous adverse effects from anticonvulsants?
Patients initiating aromatic ASMs are at highest risk, with incidence up to 17% for CBZ, PHT, PB, and LTG. Genetic factors play a key role: HLA-B*1502 increases SJS/TEN risk with CBZ in Asian populations; HLA-B*5801 with allopurinol (sometimes co-prescribed); HLA-A*3101 with CBZ in Europeans. Children and young adults experience more urticaria; overall rash rates prompt discontinuation in 15.9% over 5 years. Cross-reactivity among aromatic ASMs reaches 70% (e.g., oxcarbazepine allergy predicts CBZ reaction).
Clinical features
Mild reactions
- Maculopapular exanthema: Symmetrical erythematous macules/papules on trunk/extremities; pruritic; onset 7-14 days.
- Urticaria: Evanescent wheals; common in children/atopics; resolves quickly.
- Pruritus/Alopecia: Isolated itching or hair loss, especially with CBZ.
Severe reactions
| Reaction | Features | Incidence with ASMs |
|---|---|---|
| DRESS (Anticonvulsant Hypersensitivity Syndrome) | Fever, rash, eosinophilia, lymphadenopathy, organ involvement (liver/kidney); onset 2-8 weeks. | Up to 53% ASM-related; CBZ most common. |
| SJS/TEN | Mucosal erosions, skin detachment (<10% BSA SJS; >30% TEN); fever, Nikolsky sign. | Aromatic ASMs frequent; mortality 3.8-4%. |
| Erythema Multiforme | Target lesions; milder than SJS. | Seen with PHT/CBZ. |
| Palpable Purpura | Vasculitis-like; rare. | Leucocytoclastic angiitis on biopsy. |
Skin biopsies in severe cases show lymphocytic exocytosis, dyskeratotic cells, basal vacuolation (EM-like), or leucocytoclastic vasculitis.
Red flags indicating severe reaction
- Fever, facial edema, lymphadenopathy.
- Purpuric/blistering rash, mucous membrane erosions, positive Nikolsky sign.
- Systemic symptoms: tachycardia, hypotension, malaise.
- Erythroderma, skin tenderness, prominent upper trunk involvement.
- Lab abnormalities: eosinophilia, elevated LFTs, atypical lymphocytes.
Diagnosis
Diagnosis relies on clinical history, timing (1-8 weeks post-initiation), and exclusion of infection/malignancy. Patch testing (5% pet/aq) confirms hypersensitivity in some cases. Biopsy aids differentiation. Genetic testing (HLA) guides prophylaxis in high-risk groups. RegiSCAR score assesses DRESS probability.
Management
- Immediate discontinuation of offending ASM for any rash with red flags.
- Mild reactions: Dose reduction, monitor; topical steroids for oral lesions.
- Severe (SJS/TEN/DRESS): Hospitalize; supportive care, IVIG/cyclosporine debated; avoid systemic steroids in SJS/TEN.
- Switching ASMs: Prefer non-aromatic (valproate, levetiracetam, gabapentin, topiramate) with lower risk (0.3-1%). Desensitization rare.
Sodium valproate often tolerated post-CBZ/PHT reaction, but not universally.
Which anticonvulsants cause skin reactions?
| Drug | Risk Level | Common Reactions |
|---|---|---|
| Carbamazepine (CBZ) | High | DRESS (most common), SJS/TEN, maculopapular (5-17%). |
| Phenytoin (PHT) | High | Hypersensitivity syndrome, EM, rashes with fever. |
| Phenobarbital (PB) | High | Cross-reactive with CBZ; rashes. |
| Lamotrigine (LTG) | Moderate-High | SJS/TEN (dose-dependent); rash 5-17%. |
| Oxcarbazepine (OXC) | Moderate | 70% cross-risk with CBZ. |
| Valproate | Low | Often tolerated; rare SJS with LTG combo. |
| Gabapentin/Topiramate/Levetiracetam | Low | Mild rashes (0.3%); pruritus. |
Prevention
HLA screening in high-risk ethnicities (e.g., HLA-B*1502 Asians before CBZ). Slow titration (esp. LTG). Avoid aromatic ASM cross-switching. Educate on red flags; prompt rash reporting. FDA warns of rare serious reactions with levetiracetam/clobazam.
Patient education
Seek immediate care for rash with fever, blisters, eye pain, mouth sores, or swelling. Mild rashes may resolve but consult neurologist. Do not restart suspect drug.
Frequently Asked Questions
Q: How common are skin rashes with anticonvulsants?
A: 2-16% of patients; 5-17% with aromatic ASMs like CBZ/PHT. Most mild, but 5% severe.
Q: What is anticonvulsant hypersensitivity syndrome?
A: Also DRESS: fever, rash, eosinophilia, liver involvement; CBZ/PHT common; biopsy shows EM-like changes.
Q: Can I switch to another anticonvulsant if I have a rash?
A: Avoid aromatic cross-switch (70% risk); prefer valproate or newer ASMs like levetiracetam.
Q: Are genetic tests recommended?
A: Yes, HLA-B*1502 for CBZ in Asians to prevent SJS/TEN.
Q: When to go to ER for a rash?
A: Fever, blisters, skin pain, mucous erosions, swelling—call 911.
References
- Anticonvulsant drug hypersensitivity — PubMed/Spanish Allergy Journal. 2003. https://pubmed.ncbi.nlm.nih.gov/12926190/
- Cutaneous Reactions to Anticonvulsant Medications — Psychiatrist.com. Accessed 2026. https://www.psychiatrist.com/jcp/cutaneous-reactions-anticonvulsant-medications/
- Cutaneous Adverse Drug Reactions to Antiseizure Medications — PMC/NCBI. 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC11664053/
- Antiseizure Medications Can Cause Rare, Potentially Life-Threatening Rashes — The Derm Digest. 2024. https://thedermdigest.com/antiseizure-medications-can-cause-rare-potentially-life-threatening-rashes/
- Antiseizure Medications Can Produce Life-Threatening Reactions — Rutgers.edu. 2024. https://www.rutgers.edu/news/antiseizure-medications-can-produce-life-threatening-reactions
- FDA warns of rare but serious drug reaction to antiseizure medications levetiracetam and clobazam — FDA.gov. 2023. https://www.fda.gov/media/174157/download
- Side Effects of Seizure Medicine — Epilepsy Foundation. Accessed 2026. https://www.epilepsy.com/treatment/medicines/side-effects