
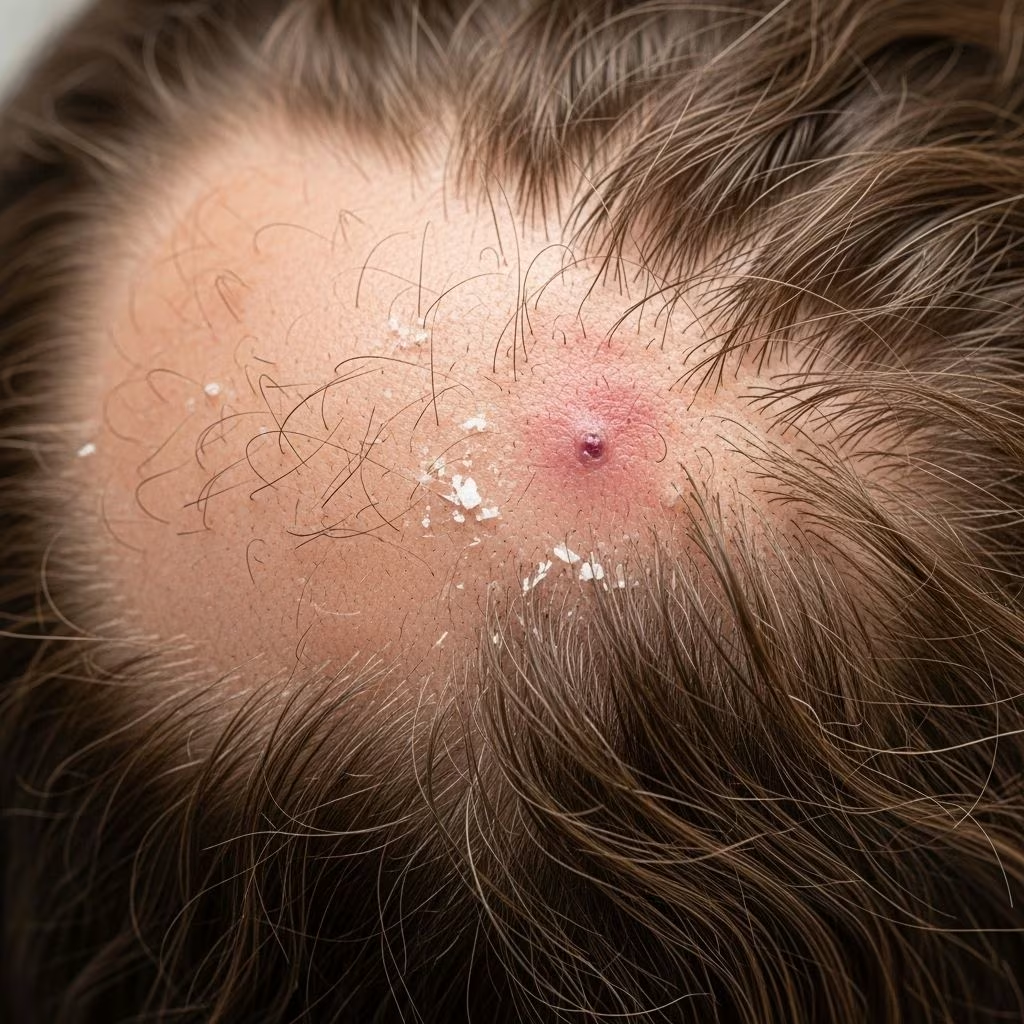
Hair loss, excessive hair growth, and various scalp conditions represent a significant portion of dermatological consultations. These disorders can be broadly categorised into hair shedding, alopecia (diffuse or localised), hair shaft abnormalities, skin diseases affecting the scalp, and excessive hair growth such as hirsutism or hypertrichosis. Understanding the hair growth cycle—anagen (growth), catagen (transition), and telogen (resting)—is fundamental, as disruptions in these phases underlie many conditions.
Introduction
Hair serves protective, sensory, and thermoregulatory functions, with the scalp hosting approximately 100,000 follicles. Normal daily shedding ranges from 50-100 hairs, but excessive loss or growth signals pathology. Balding may be scarring (permanent follicle destruction) or non-scarring (reversible). Scalp evaluation involves assessing oiliness, lesions, inflammation, and hair pull tests. Diffuse thinning often stems from pattern balding, while localised patches suggest alopecia areata or infections. This article covers diagnosis, causes, and management comprehensively.
Hair Shedding
Hair shedding is a normal physiological process but becomes pathological when excessive, leading to visible scalp exposure. Acute events like surgery, illness, or medications trigger telogen effluvium, where up to 90% of anagen hairs enter telogen prematurely, causing diffuse shedding 2-3 months post-event. Anagen effluvium, seen in chemotherapy, results in brittle, fractured hairs due to mitotic arrest in growing follicles.
Chronic telogen effluvium mimics female pattern hair loss but is distinguished by pull tests yielding telogen hairs. Management focuses on addressing triggers: iron supplementation for deficiency, thyroid correction, or stress reduction. In severe cases, shedding progresses to baldness if untreated.
Diffuse Alopecia
Diffuse alopecia involves widespread thinning without distinct patches. In men, androgenetic alopecia (male pattern baldness) features frontal recession and vertex thinning due to dihydrotestosterone sensitivity. Women experience female pattern hair loss (FPHL) with central parting widening, sparing the frontal hairline.
Other causes include systemic lupus erythematosus, syphilis, iron deficiency (thin fragile hair), or hypothyroidism (coarse dry hair). Adolescents rarely present with pattern balding; suspect nutritional or endocrine issues. Diagnosis employs trichoscopy showing miniaturized hairs and scalp biopsy if needed. Treatments: minoxidil topically, finasteride orally (men), spironolactone (women), or low-level laser therapy.
Localised Alopecia
Localised alopecia manifests as patches of baldness. Alopecia areata, an autoimmune disorder, causes round, smooth patches with exclamation mark hairs (short, tapered broken stubs). It affects 2% lifetime risk, associating with atopy, thyroid disease, vitiligo, or Down syndrome. Variants: alopecia totalis (scalp), universalis (body-wide), or ophiasis (occipital band).
Inflammatory patches with erythema, scaling, or pustules in children suggest tinea capitis (fungal, with kerion), folliculitis, or psoriasis. Scarring alopecia (cicatricial) shows shiny pale skin, absent follicles: lichen planopilaris, discoid lupus, or folliculitis decalvans. Traction alopecia from tight hairstyles affects frontal margins, reversible if early. Trichotillomania presents asymmetrical broken hairs from plucking, managed with CBT.
| Condition | Features | Scarring? |
|---|---|---|
| Alopecia areata | Smooth round patches, exclamation hairs | No |
| Tinea capitis | Scaling, pustules, hair breakage | Possible |
| Lichen planopilaris | Perifollicular erythema, scarring | Yes |
| Traction alopecia | Frontal fringe loss | No (early) |
Hair Shaft Abnormalities
Hair shaft disorders are rare genetic conditions diagnosed via light/electron microscopy or dermoscopy, presenting in infancy with short, unruly, or fragile hair. Common types:
- Trichorrhexis nodosa: Node-like swellings leading to breakage from trauma or argininosuccinic aciduria.
- Monilethrix: Beaded, elliptical shafts with periodic fragility.
- Pili torti: Twisted, flattened shafts in Menkes disease or ectodermal dysplasia.
- Uncombable hair syndrome: Spun-glass appearance due to longitudinal grooving.
Management is supportive: gentle care, avoid trauma. Biotin or cysteine supplements may help select cases.
Skin Diseases Affecting the Scalp
Scalp skin diseases often cause itch, scaling, or inflammation, sometimes with secondary alopecia. Evaluate for oiliness, plaques, or pustules.
| Condition | Clinical Features |
|---|---|
| Dandruff (pityriasis capitis) | Diffuse fine scaling |
| Seborrhoeic dermatitis | Yellowish greasy plaques, flexures |
| Psoriasis | Well-defined erythematous plaques, silvery scale |
| Pityriasis amiantacea | Sticky asbestos-like scale (psoriasis/seborrhoea) |
| Head lice | Nits, excoriations |
| Lichen simplex | Lichenified itchy plaques (occiput) |
| Folliculitis | Pustules around follicles |
Treatment: antifungals/shampoos for dandruff/seborrhoea (ketoconazole), coal tar for psoriasis, pediculicides for lice.
Excessive Hair Growth
Hirsutism is androgen-dependent male-pattern hair in women (face, chest, abdomen). Causes: PCOS (80%), idiopathic, or tumours. Hypertrichosis is non-androgenetic excess lanugo/terminal hair, congenital or acquired (drugs, malnutrition).
Investigate hormones (testosterone, DHEAS). Treatments:
- Physical: Shaving, waxing, electrolysis, IPL, laser.
- Medical: Spironolactone, cyproterone acetate, eflornithine cream.
Hirsutism may coexist with scalp thinning mimicking male pattern.
Frequently Asked Questions (FAQs)
Q: What causes sudden hair shedding?
A: Telogen effluvium from stress, illness, or medications; resolves by addressing trigger.
Q: Is alopecia areata permanent?
A: Often regrows spontaneously; totalis/universalis less favourable, treat with corticosteroids.
Q: How to differentiate FPHL from telogen effluvium?
A: Biopsy or trichoscopy; FPHL shows miniaturization, chronic effluvium excessive shedding.
Q: Can scalp conditions cause permanent baldness?
A: Yes, scarring alopecias like lichen planopilaris destroy follicles.
Q: What are safe treatments for hirsutism?
A: Anti-androgens after excluding pregnancy; cosmetic removal for hypertrichosis.
Q: When to see a dermatologist for hair loss?
A: Patchy loss, rapid shedding, associated scalp symptoms, or no improvement with OTC.
Wigs are subsidised for medically necessary cases. Seek evidence-based advice; avoid unproven remedies.
References
- Follicular disorders. Disorders of the hair and scalp — DermNet NZ. 2009 (updated). https://dermnetnz.org/cme/follicular/disorders-of-the-hair-and-scalp
- Principles of dermatological practice. Examination of hair and scalp — DermNet NZ. https://dermnetnz.org/cme/principles/examination-of-hair-and-scalp
- Hair loss — DermNet NZ. https://dermnetnz.org/topics/hair-loss
- Hair Disorders — Geeky Medics. https://geekymedics.com/hair-disorders/
- Hair shedding — DermNet NZ. https://dermnetnz.org/topics/hair-shedding
- Female pattern hair loss — DermNet NZ. https://dermnetnz.org/topics/female-pattern-hair-loss
- Diagnosis of scalp rashes — DermNet NZ. https://dermnetnz.org/topics/diagnosis-of-scalp-rashes



