
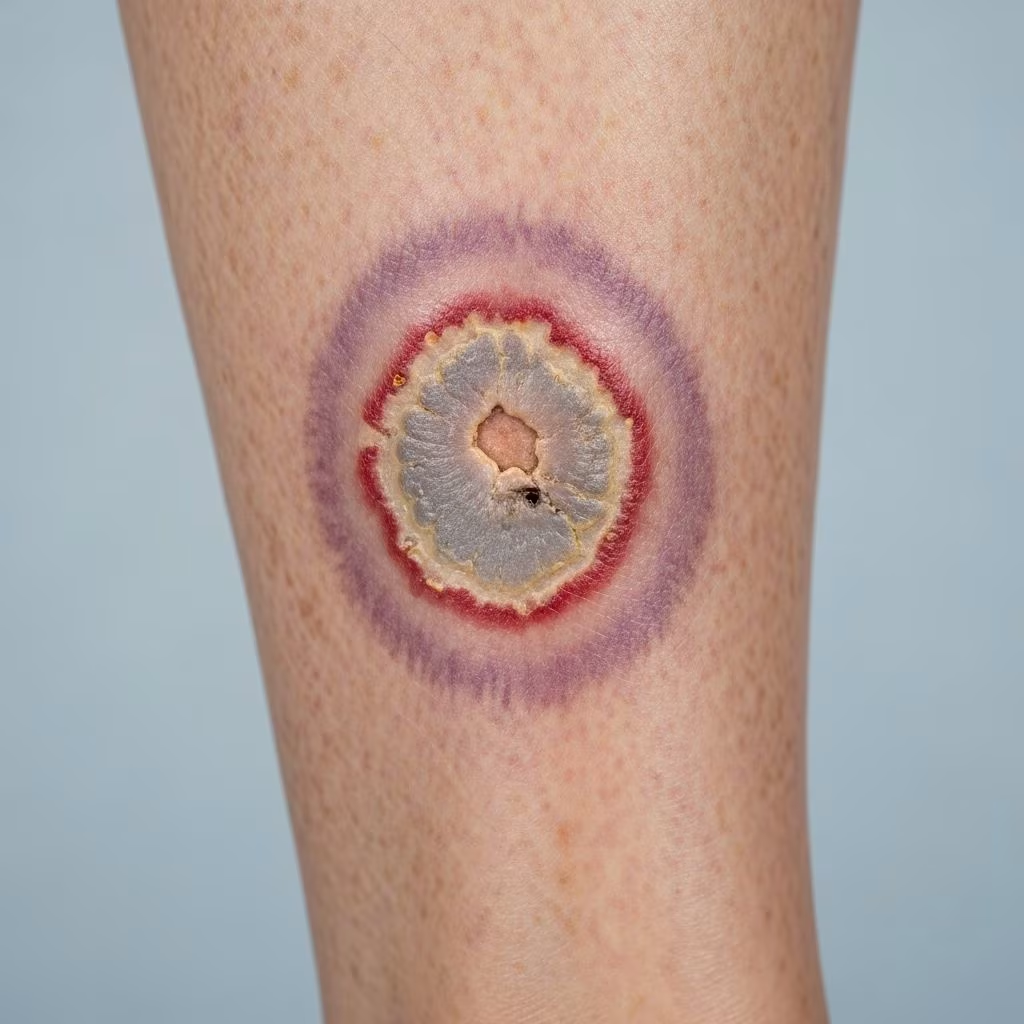
Martorell ulcer, also known as hypertensive ischemic leg ulcer (HYTILU), is a rare but severe form of lower leg ulceration caused by longstanding, poorly controlled hypertension leading to obstruction of small dermal arterioles. First described by Fernando Martorell Otzet in 1945, this condition primarily affects women aged 50-70 years and presents with excruciating pain disproportionate to the lesion size, necrotic base, and violaceous edges. Unlike common venous or arterial ulcers, Martorell ulcers arise from microvascular changes rather than large vessel disease, making early recognition critical to prevent chronic wounds and disability.
What is Martorell Ulcer?
Martorell ulcer represents an underdiagnosed cause of leg ulcers, accounting for approximately 1.3-7% of all lower extremity ulcers in specialized wound centers. It manifests as punched-out, deep ulcers typically located on the dorsolateral aspect of the lower leg, often with satellite pustules or purpura. The hallmark is intense pain that fails to respond to standard analgesics, reflecting underlying tissue ischemia from arteriolar hyalinization and luminal narrowing.
Patients usually have a history of severe hypertension (>160/100 mmHg) for over 10 years, with target organ damage evident in retinas, heart, kidneys, or brain. The ulcer may develop spontaneously or after minor trauma, progressing rapidly to necrosis despite normal ankle-brachial index (ABI), which differentiates it from macrovascular peripheral artery disease.
Who Gets Martorell Ulcer?
This condition predominantly affects middle-aged to elderly women (female-to-male ratio ~3:1), with mean age at diagnosis around 60-70 years. Key risk factors include:
- Uncontrolled systemic arterial hypertension (essential in >90% of cases)
- Obesity and metabolic syndrome
- Smoking history
- Dyslipidemia
- Type 2 diabetes mellitus (comorbid in ~30-50%)
Importantly, large-vessel arterial disease is absent in most patients, with normal arterial pulses and ABI >0.9. Ethnic predisposition is not well-established, but cases are reported globally, often in hypertensive populations.
Causes
The pathogenesis involves chronic shear stress from elevated blood pressure causing endothelial dysfunction in dermal and subcutaneous arterioles. This leads to intimal hyperplasia, medial hypertrophy, and hyalinization, reducing luminal diameter by up to 80% and impairing nutritive blood flow to the skin.
Key pathophysiological mechanisms:
- Arteriolar hyalinization: Deposition of hyaline material in vessel walls, unique to hypertensive vasculopathy.
- Hyperplasia of vascular smooth muscle: Thickening of the tunica media in response to pulsatile hypertension.
- Endothelial remodeling: Stimulated by shear stress, leading to luminal obliteration.
- Microthrombosis: Secondary platelet aggregation in narrowed vessels.
Minor trauma may precipitate ulceration in 50% of cases, but spontaneous infarction occurs due to critical ischemia.
Signs and Symptoms
Martorell ulcers are characterized by:
- Severe, burning pain: Disproportionate to ulcer size, often requiring opioids; worsens with leg dependency.
- Location: Anterolateral or dorsolateral lower leg (60-80%), occasionally thigh or foot.
- Morphology: Punched-out ulcer 1-5 cm diameter, necrotic black eschar base, undermined violaceous edges; satellite lesions common.
- Surrounding skin: Indurated, livedo-like purpura, or reticularis pattern.
- Systemic: Elevated inflammatory markers (CRP, WBC); normal pulses.
Pain prevents sleep and daily activities, with hyperpulsatile femoral/dorsalis pedis arteries due to increased vascular resistance distally.
Diagnosis
Diagnosis is primarily clinical, supported by exclusion of differentials and histopathology. Key diagnostic criteria (Hafner et al.) include:
| Criterion | Description |
|---|---|
| 1. Hypertensive emergency | SBP >160 mmHg and/or DBP >100 mmHg |
| 2. Normal ABI (>0.9) | Excludes large-vessel PAD |
| 3. Ulcer on lateral lower leg | Typical location |
| 4. Severe pain | Resistant to standard analgesics |
| 5. Arteriolar hyalinization on biopsy | Pathognomonic |
| 6. No vasculitis/large vessel disease | On histopathology/Doppler |
| 7. Response to BP control | Pain/ulcer improvement |
Investigations:
- Blood pressure measurement (both arms)
- Duplex ultrasound/Doppler (rule out venous/arterial disease)
- ABI/toe pressure
- Skin biopsy (essential for confirmation)
- Labs: CRP, ESR, CBC, renal function, coagulation profile
Histopathology shows endothelial swelling, hyalinized arterioles without calcification (vs. calciphylaxis) or leukocytoclastic vasculitis (vs. pyoderma gangrenosum).
Differential Diagnosis
Martorell ulcer must be distinguished from:
| Condition | Key Differentiators |
|---|---|
| Pyoderma gangrenosum | Rapid progression, pathergy, undermined edges, neutrophil infiltrate; immunosuppression worsens Martorell |
| Calciphylaxis | Renal failure, livedo reticularis, calcium deposits on biopsy, proximal location |
| Venous ulcer | Medial malleolar, stasis dermatitis, venous reflux on duplex |
| Arterial ulcer | Low ABI (<0.9), claudication, absent pulses |
| Diabetic neuropathic ulcer | Pressure points, sensory loss, good pulses |
Treatment
Treatment is multimodal, focusing on blood pressure optimization, analgesia, and wound care.
Pain Management
Excruciating pain requires:
- Stepwise analgesia: Paracetamol/NSAIDs → opioids (morphine/fentanyl patches) → spinal cord stimulation for refractory cases.
- Leg elevation and cooling.
- Avoid beta-blockers (worsen perfusion).
Blood Pressure Control
Achieve BP <140/90 mmHg using calcium channel blockers (e.g., amlodipine) and ACE inhibitors (e.g., lisinopril); anticoagulate with heparin.
Wound Care
- Debridement of necrotic tissue (bedside or surgical).
- Negative pressure wound therapy (NPWT).
- Moist dressings (petrolatum, silver-impregnated for infection).
- Antibiotics for secondary infection.
Surgical Intervention
Early surgery for ulcers >3 cm:
- Sharp debridement + split-thickness skin grafting (success in 90%).
- Lumbar sympathectomy (variable benefit for pain/perfusion).
Healing occurs in 70-90% with combined therapy, though recurrence risk is 20-30% without BP control.
Prevention
Preventive strategies target hypertension management:
- Rigorous BP control (<130/80 mmHg ideally).
- Smoking cessation.
- Weight loss and exercise.
- Avoid trauma to lower legs.
- Regular skin checks in high-risk hypertensives.
Outlook
With early diagnosis and treatment, complete healing is achieved in most cases within 4-12 weeks. Delayed diagnosis leads to prolonged pain, infection, and amputation risk (rare). Recurrence is prevented by sustained BP control. Misdiagnosis as inflammatory ulcer with immunosuppression carries poor prognosis.
Frequently Asked Questions
What causes Martorell ulcer?
Martorell ulcer results from arteriolar damage due to chronic, uncontrolled high blood pressure, leading to skin ischemia and ulceration.
How painful is Martorell ulcer?
Extremely painful, often described as burning and unresponsive to regular painkillers, requiring opioids or advanced therapies.
Can Martorell ulcer be cured?
Yes, with blood pressure control, debridement, and skin grafting, most ulcers heal completely, though prevention of recurrence is key.
Is surgery necessary for Martorell ulcer?
Surgery is recommended for larger ulcers (>3 cm) to promote rapid healing and pain relief.
How do you differentiate Martorell ulcer from pyoderma gangrenosum?
Martorell shows vascular changes on biopsy and responds to BP control; pyoderma has neutrophilic infiltrate and pathergy. Immunosuppression harms Martorell ulcers.
References
- Martorell’s Ulcer: Diagnostic and Therapeutic Challenge — Rodrigues D, et al. PMC – NIH. 2015-08-26. https://pmc.ncbi.nlm.nih.gov/articles/PMC4560305/
- Martorell ulcer: chronic wound management and rehabilitation — Alavi A, et al. Dove Press. 2018-06-12. https://www.dovepress.com/martorell-ulcer-chronic-wound-management-and-rehabilitation-peer-reviewed-fulltext-article-CWCMR
- Martorell Hypertensive Ischemic Leg Ulcer: An Underdiagnosed Entity — Nappi J. Nursing2022. 2012-12-01. https://nursing.ceconnection.com/ovidfiles/00129334-201212000-00010.pdf
- Martorell ulcer — DermNet NZ. 2023. https://dermnetnz.org/topics/martorell-ulcer
- Martorell hypertensive leg ulcer — VisualDx. 2024. https://www.visualdx.com/visualdx/diagnosis/martorell+hypertensive+leg+ulcer?diagnosisId=54939&moduleId=101



