
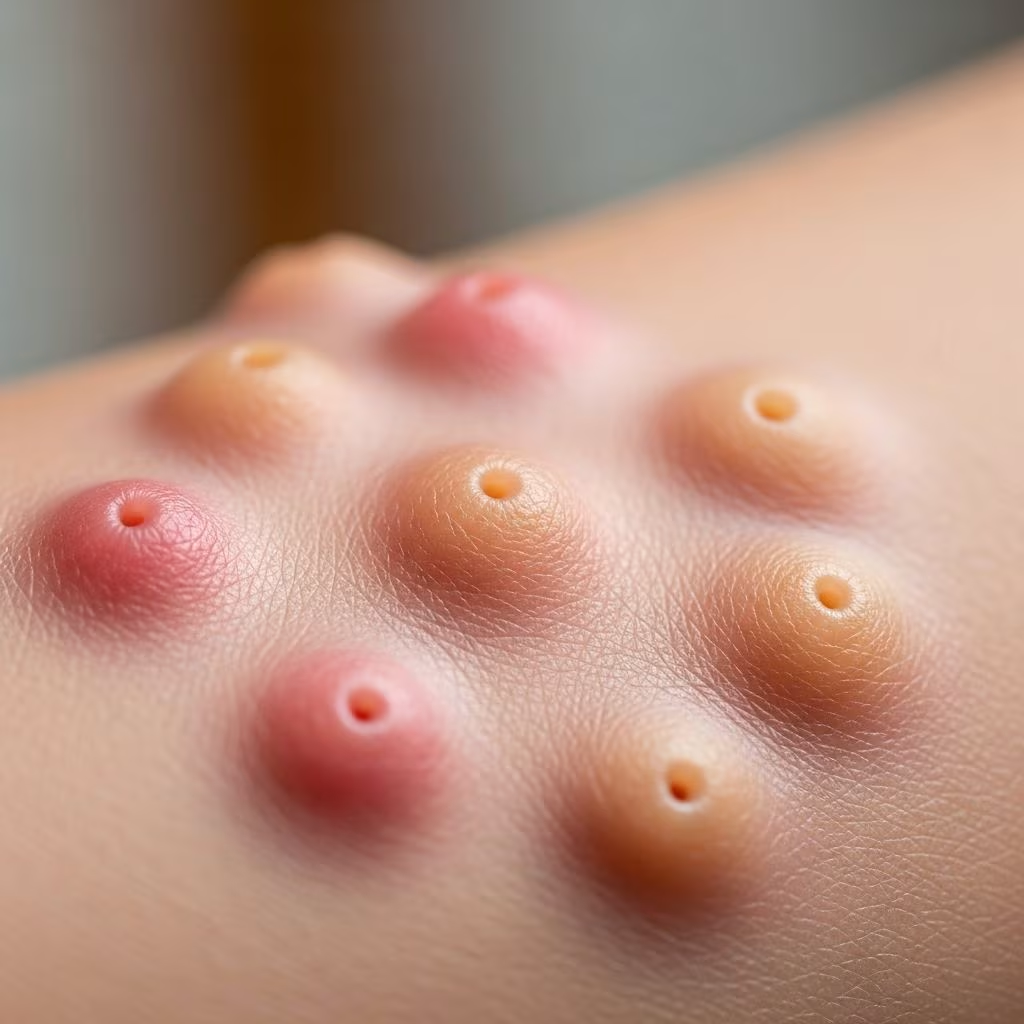
Molluscum contagiosum is a common benign cutaneous infection caused by a poxvirus, primarily affecting children but also occurring in adults, particularly through sexual transmission. It presents as multiple soft, umbilicated papules and often provokes localised eczema, especially in atopic individuals.
Who gets molluscum contagiosum?
Molluscum contagiosum predominantly affects children aged 1–10 years, with higher incidence in tropical climates and among those with atopic dermatitis. In adults, it is frequently sexually transmitted, appearing on genitals and lower abdomen. Immunocompromised patients, such as those with HIV, may develop extensive, persistent lesions. Atopic eczema increases susceptibility due to impaired skin barrier function.
Transmission
The molluscum contagiosum virus (MCV), a double-stranded DNA poxvirus, spreads via direct skin-to-skin contact, including sexual contact, or indirectly through contaminated objects like towels, toys, or sports equipment. Autoinoculation occurs when scratching spreads the virus to adjacent skin. Transmission is more likely in wet environments, such as swimming pools or baths. The incubation period ranges from 2 weeks to 6 months, typically 2–8 weeks.
- Direct skin-to-skin contact
- Fomites (towels, clothing, sponges)
- Autoinoculation from scratching
- Shared wet environments (pools, baths)
Clinical features
Lesions are small (1–6 mm, occasionally up to 20 mm), round, firm, dome-shaped papules with a pearly-white, pink, or skin-colored surface and characteristic central umbilication (dimple). They contain white, cheesy molluscum bodies (Henderson-Paterson bodies) expressible from the center. Common sites in children: face, trunk, axillae, arms, upper legs. In adults: genitals, thighs, lower abdomen. Number varies from 1–20 typically, but hundreds in immunocompromised cases. Surrounding eczema (molluscum dermatitis) is common, causing itchiness.
As lesions resolve spontaneously (months to 2 years), they may inflame (red, crusted), become necrotic (black scabs), or leave punctate scars.
Complications
- Molluscum dermatitis: Eczematous reaction around lesions, especially in atopics, leading to secondary bacterial infection
- Secondary infection: Bacterial superinfection from scratching
- Scarring: Punctate scars post-resolution
- Giant molluscum: Lesions >1 cm, more common in HIV
- Extensive disease: In immunocompromised patients
Diagnosis
Diagnosis is clinical based on characteristic umbilicated papules. Dermoscopy reveals central white-yellow amorphous area with peripheral vessels. Expressing cheesy material confirms molluscum bodies. In atypical cases (e.g., immunocompromised), biopsy shows cup-shaped epidermal invagination, acanthosis, and Henderson-Paterson bodies. Reflectance confocal microscopy or histopathology aids if needed.
| Diagnostic Method | Key Features |
|---|---|
| Clinical exam | Umbilicated papules 2–5 mm |
| Dermoscopy | Central white core, vascular crown |
| Expression | White molluscum bodies |
| Biopsy | Henderson-Paterson bodies |
Differential diagnosis
- Cryptic warts (no umbilication)
- Milker’s nodules (paravaccinia)
- Pyogenic granuloma
- Basal cell carcinoma (in adults)
- Trichilemmoma
- Pediculosis corporis (bites)
Treatment of molluscum contagiosum
In immunocompetent children, treatment is often unnecessary as 50% resolve by 12 months, 66% by 18 months. Treat to prevent spread, reduce duration, or alleviate symptoms (itch, eczema). Options include physical destruction, topical irritants, antivirals. No single best treatment; choice depends on age, number/site of lesions, patient preference.
Physical treatments
- Curettage: Scrape lesions after EMLA anesthesia (pea-sized per lesion, occlude 60 min). Use 3mm curette. Risks: scarring, pigment change
- Cryotherapy: Liquid nitrogen 5–10 sec, 1–2 cycles. Repeat 2–4 weeks. Risks: pain, blistering, hypopigmentation
- Laser: Pulsed dye laser for recalcitrant cases
Topical treatments
| Agent | Regimen | Notes |
|---|---|---|
| Potassium hydroxide 5–10% (MolluDab) | BID until inflammation, max 2 weeks | Irritant; stop on response |
| Salicylic acid 17% | BID | OTC option |
| Podophyllotoxin 0.5% | BID 3 days/week | Genital use |
| Imiquimod 5% | 3–5x/week | Immunostimulant; for immunocompromised |
| Hydrogen peroxide 45% | Daily | Newer option |
| Benzoyl peroxide | Daily | Mild irritant |
Manage surrounding eczema: Topical corticosteroid (e.g., hydrocortisone 1% BID) + emollient BID.
Treatment in special populations
- Immunocompromised: Aggressive treatment (cryo, curettage, imiquimod, cidofovir intralesional/systemic). Monitor for dissemination
- Infants: Avoid irritants; observe or gentle curettage
- Genital in adults: Podophyllotoxin or imiquimod; partner notification
Prevention
- Wash hands frequently
- Avoid scratching/rubbing lesions
- Cover lesions with watertight bandages (esp. swimming)
- Don’t share towels, clothing, toys
- Clean shared equipment
- Treat eczema to reduce autoinoculation
Infected children may attend school/daycare; no exclusion required.
Guidelines for dermatology referral
- Immunocompromised patients
- Rapidly spreading/extensive/painful lesions
- Giant molluscum (>1 cm)
- Failure to respond to primary care treatment
- Facial/eyelid lesions
- Diagnostic uncertainty
Frequently Asked Questions (FAQs)
Q: Is molluscum contagiosum contagious?
A: Yes, highly contagious via skin contact, fomites, autoinoculation until lesions resolve.
Q: How long does molluscum contagiosum last?
A: 6–12 months typically; up to 2–4 years. Treats faster with intervention.
Q: Should I treat molluscum in children?
A: Optional; treat if spreading, symptomatic, or cosmetic concern. No treatment in asymptomatic cases.
Q: Can molluscum scar?
A: Rarely; inflamed/resolving lesions may leave punctate scars. Treatment risks scarring.
Q: Is there a vaccine for molluscum?
A: No; canarypox vaccine studied experimentally.
References
- Molluscum Contagiosum — Montreal Children’s Hospital. 2021-09. https://montrealchildrenshospital.ca/wp-content/uploads/2021/09/molluscum_md_2021.pdf
- Molluscum contagiosum – CME — DermNet NZ. Accessed 2026. https://dermnetnz.org/cme/viral-infections/molluscum-contagiosum-cme
- Molluscum Contagiosum Patient Information Leaflet — Skin Health Info. 2025-01. https://www.skinhealthinfo.org.uk/wp-content/uploads/2018/11/Molluscum-contagiosum-PIL-Jan-2025.pdf
- Molluscum Contagiosum — Patient.info. Accessed 2026. https://patient.info/childrens-health/viral-skin-infections-leaflet/molluscum-contagiosum
- Molluscum contagiosum — DermNet NZ. Accessed 2026. https://dermnetnz.org/topics/molluscum-contagiosum
- Molluscum Contagiosum — StatPearls, NCBI Bookshelf. 2023. https://www.ncbi.nlm.nih.gov/books/NBK441898/



