
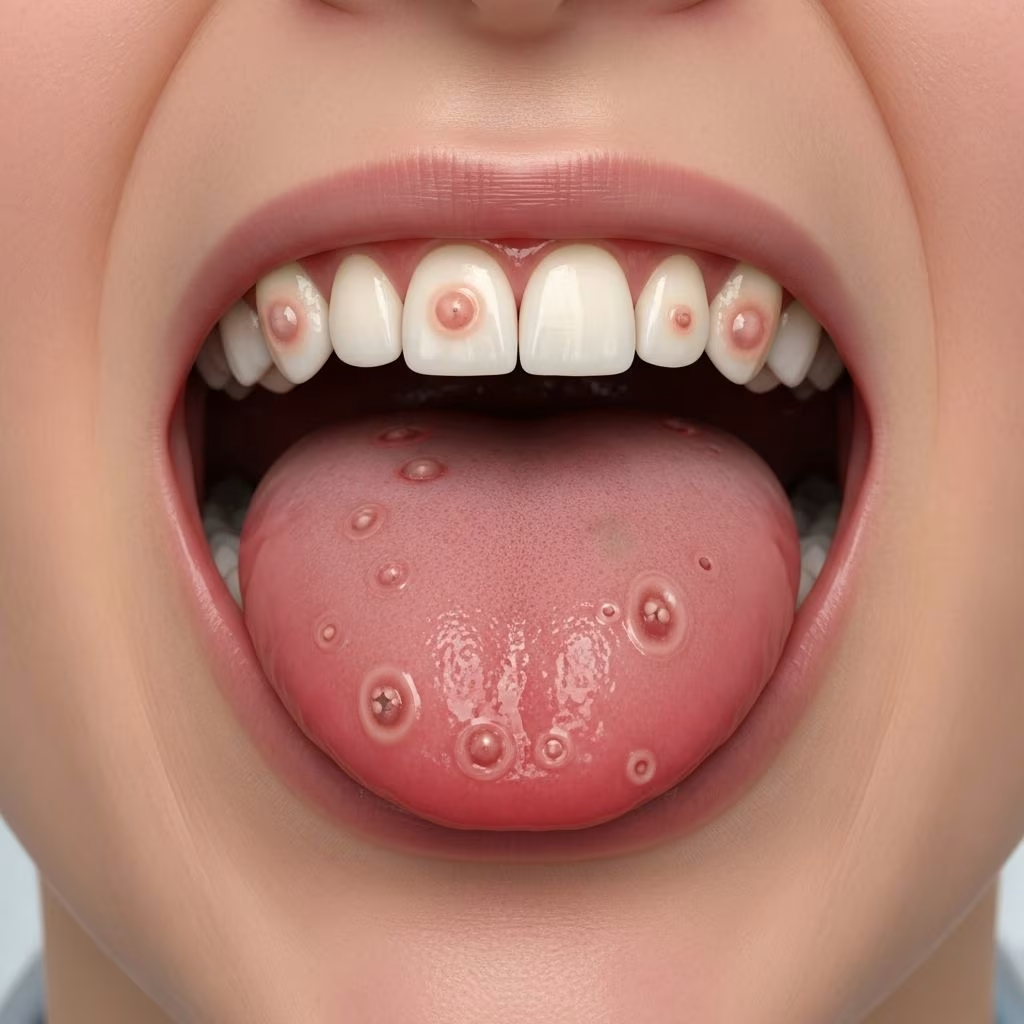
Inflammatory bowel disease (IBD) encompasses Crohn disease and ulcerative colitis, chronic conditions affecting the gastrointestinal tract. Both can manifest orally, though more frequently and severely in Crohn disease. These oral changes may precede intestinal symptoms, aiding early diagnosis, or coincide with disease flares.
Oral involvement occurs in up to one-third of Crohn patients, higher in children, sometimes preceding bowel diagnosis by months or years. A male predominance is noted in some studies. Facial and oral changes categorize into specific (diagnostic histology), nonspecific reactive, nutritional deficiency-related, and drug-induced effects. The first three categories often guide clinicians toward IBD investigation.
What are the changes of the face and oral mucosa associated with inflammatory bowel disease?
Changes divide into four categories:
- Specific oral mucosal changes: Granulomatous, mirroring intestinal pathology.
- Nonspecific changes in mouth and facial skin: Reactive to inflammation.
- Nutritional deficiency signs: From malabsorption or reduced intake.
- Drug-induced oral effects: Side effects of IBD therapies.
Specific changes are diagnostically valuable via biopsy showing non-caseating granulomas.
Crohn disease
The oral mucosa is commonly affected in Crohn disease, with up to 33% of adults and higher rates in children showing changes. In 60% of pediatric cases, oral lesions precede bowel diagnosis.
Specific oral mucosal changes: orofacial Crohn disease
Orofacial Crohn disease represents granulomatous inflammation of the oral cavity and face, a specific IBD manifestation. In children, it often precedes intestinal involvement.
Clinical features include:
- Cobblestoning: Fissured, swollen mucosa with hyperplastic corrugation, typically posterior buccal mucosa.
- Indurated tag-like lesions: Firm, hyperplastic edges in labial/buccal vestibules or retromolar areas.
- Mucogingivitis: Edematous, granular, hyperplastic gingiva up to mucogingival line, with or without ulcers.
- Lip swelling: Painless, tender, firm edema, often with vertical fissures; microbes may colonize fissures.
- Deep linear ulcers: In lips, tongue, buccal sulci.
- Facial edema: Perioral swelling.
Common sites: lips, buccal mucosa, gingiva. Other features: erythema, fissures, pustules, ulceration. Severe lip ulcers may signal drug reactions like Stevens-Johnson syndrome. Biopsy confirms non-caseating granulomas.
Nonspecific changes in the mouth and surrounding facial skin associated with Crohn disease
Nonspecific manifestations include:
- Aphthous stomatitis: Shallow, round ulcers with erythematous borders anywhere in the mouth.
- Angular cheilitis: Erythema, fissures at mouth corners.
- Glossitis: Tongue inflammation, atrophy, pallor from deficiencies.
- Perioral dermatitis, recurrent abscesses, salivary duct fistulas, submandibular lymphadenopathy.
- Periodontitis, dental caries: Due to poor hygiene or drugs.
These may persist despite intestinal remission, especially in children.
Ulcerative colitis
Oral changes are less common in ulcerative colitis than Crohn, mostly nonspecific; specific changes are rare. In children, only nonspecific findings noted in large studies.
Specific orofacial changes of ulcerative colitis: pyostomatitis vegetans
Pyostomatitis vegetans (PV) is a rare specific lesion in ulcerative colitis, featuring erythematous, thickened mucosa with pustules, superficial erosions, and ‘snail-track’ fissures after pustule rupture. Sites: labial gingiva, buccal/labial mucosa, palate; less often tongue. Oral ulcers and malodor possible. Biopsy shows intraepithelial clefting, acantholysis, eosinophilic microabscesses. Differential: pemphigoid, infections.
Nonspecific changes of the mouth and surrounding skin associated with ulcerative colitis
Include aphthous ulcers, angular cheilitis, glossitis, similar to Crohn but milder.
Nutritional deficiencies
Malabsorption in IBD arises from diarrhea, reduced intake, bacterial overgrowth, surgery, disease, or drugs, causing oral signs.
| Nutrient | Oral Manifestations |
|---|---|
| Iron | Pallor, glossitis, angular cheilitis |
| Vitamin B12/folate | Glossitis, cheilitis, ulcers, taste changes |
| Vitamin C | Bleeding gums, poor healing |
| Zinc | Glossitis, ulcers, taste loss |
| Others | Dry mouth (salivary gland involvement) |
Deficiencies contribute to tongue atrophy, ulcers, pallor.
Drugs
IBD medications frequently cause oral side effects.
| Drug | Oral Side Effects |
|---|---|
| Cholestyramine | Tongue irritation, sour taste, bleeding, caries, enamel erosion, discoloration |
| Ciprofloxacin | Candidiasis, angioedema, SJS/TEN, taste loss |
| Colestipol | Dysphagia |
| Diphenoxylate/atropine | Dry mouth, lip swelling, taste changes |
| Infliximab | Infections, angioedema |
| Loperamide | Dry mouth, SJS/TEN, angioedema |
| Mesalazine | Sore throat, candidiasis, dry mouth, stomatitis, taste alteration |
| Methotrexate | Stomatitis, gingivitis, pharyngitis |
| Metronidazole | Metallic taste, furry tongue, glossitis, stomatitis, candidiasis, dry mouth |
| Prednis(ol)one | Oral candidiasis (thrush) |
| Propantheline | Dry mouth, angioedema, taste loss |
| Sulphasalazine | Stomatitis, SJS/TEN, taste changes, folate malabsorption |
Sulfasalazine, thiopurines, anti-TNF agents linked to lichenoid reactions.
Management
Treatment targets underlying IBD; oral lesions often improve with disease control. Persistent specific lesions (e.g., orofacial Crohn) may need topical corticosteroids (gel/mouthwash); severe cases require systemic steroids. Biopsy confirms diagnosis. OEIMs may necessitate IBD therapy escalation. Nutritional supplementation addresses deficiencies. Manage drug side effects by switching agents or supportive care (e.g., antifungals for thrush).
Frequently Asked Questions (FAQs)
Q: Can oral changes precede IBD diagnosis?
A: Yes, especially in Crohn disease children, where 60% show oral lesions first.
Q: What is the most common oral site in orofacial Crohn?
A: Lips, buccal mucosa, gingiva with cobblestoning, swelling, ulcers.
Q: How is pyostomatitis vegetans diagnosed?
A: By biopsy showing eosinophilic microabscesses, acantholysis; linked to ulcerative colitis.
Q: Do IBD drugs cause oral problems?
A: Commonly; e.g., steroids cause thrush, antibiotics candidiasis, resins caries.
Q: Can nutritional issues cause oral signs in IBD?
A: Yes, iron/B12 deficiency leads to glossitis, cheilitis, ulcers.
References
- Oral manifestations of inflammatory bowel disease — DermNet NZ. 2023. https://dermnetnz.org/topics/oral-manifestations-of-inflammatory-bowel-disease
- Guidelines for the Diagnosis and Management of Oral Lesions in Pediatric IBD — Gastroenterology Advisor. 2024-01-15. https://www.gastroenterologyadvisor.com/features/management-of-eims-in-pediatric-patients-with-ibd/
- Oral Manifestations of Inflammatory Bowel Disease and the Role of Inflammation — PMC (Front Dent. 2020). 2020-07-02. https://pmc.ncbi.nlm.nih.gov/articles/PMC7345678/
- Oral Extraintestinal Manifestations of Inflammatory Bowel Disease — Oxford Academic (Crohn’s & Colitis 360). 2025-04-01. https://academic.oup.com/crohnscolitis360/article/7/2/otaf027/8102808



