
Introduction
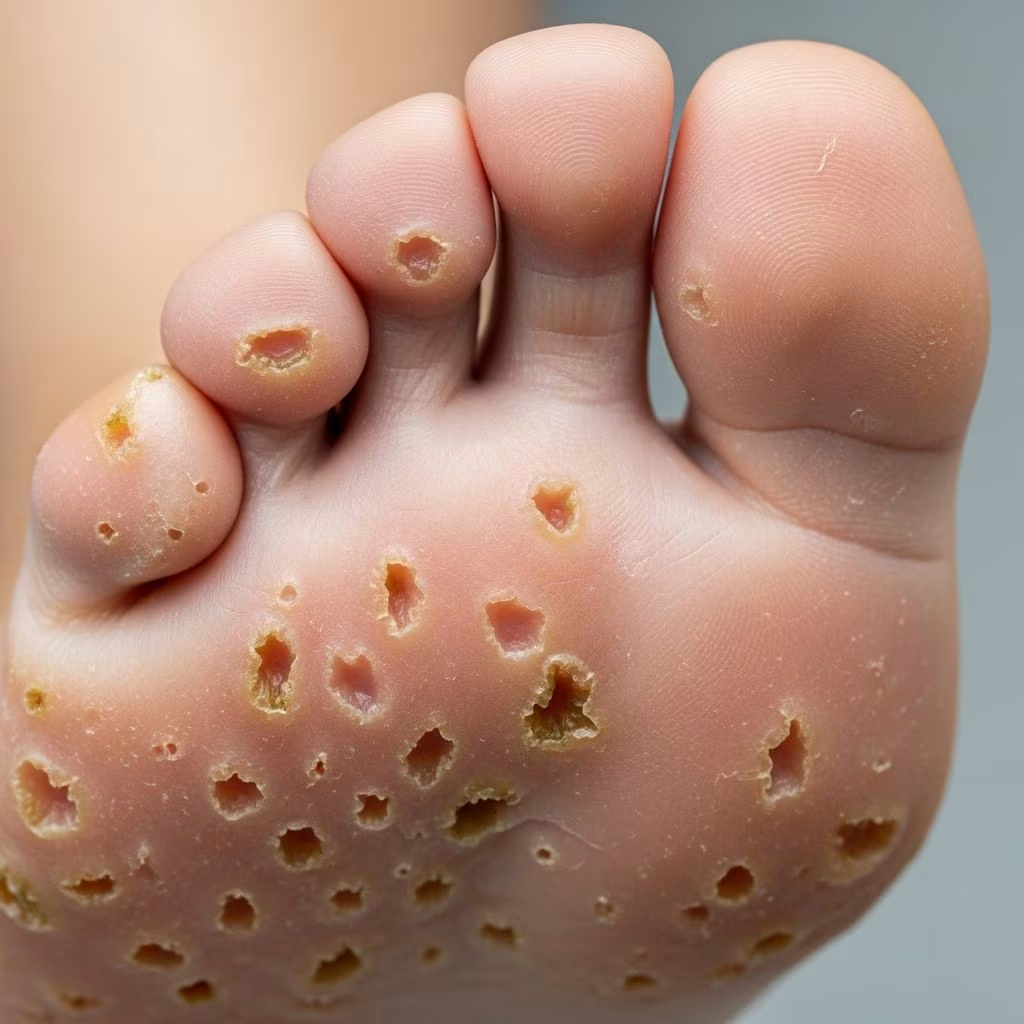
Pitted keratolysis, also known as keratolysis plantare sulcatum, keratoma plantare sulcatum, or ringed keratolysis, is a common superficial bacterial skin infection primarily affecting the feet. This condition is characterized by the formation of crater-like pits on the soles, particularly in weight-bearing areas, accompanied by a distinctive malodorous smell due to bacterial activity. It results from the overgrowth of normal skin flora under specific environmental conditions, leading to the enzymatic degradation of the stratum corneum, the outermost layer of the skin.
While generally benign and not contagious, pitted keratolysis can cause significant discomfort, social embarrassment from the odour, and occasional pain during walking. It is prevalent among individuals who experience excessive foot sweating (hyperhidrosis) and wear occlusive footwear, such as athletes, military personnel, and workers in humid professions like farming. Early recognition and simple preventive measures can effectively manage this condition, preventing recurrence.
Demographics
Pitted keratolysis predominantly affects males, with studies indicating a higher incidence in men, possibly due to occupational factors and footwear habits. It is more common in young adults and those in tropical or humid climates where moisture retention is high. Professions involving prolonged standing, occlusive shoes, or barefoot activity in moist environments—such as soldiers, athletes, farmers (e.g., rice paddy workers), and factory workers—are at elevated risk.
The condition is observed worldwide but shows increased prevalence in regions with hot, humid weather. Certain populations, including those who are overweight, diabetic, immunocompromised, or with poor hygiene, exhibit higher susceptibility. Genetic factors may play a role, as familial cases suggest shared hygienic or environmental influences. Although rare, palmar involvement occurs in specific occupational groups like agricultural workers.
Causes
The primary cause of pitted keratolysis is the overgrowth of keratin-degrading bacteria on the skin surface, particularly species of Corynebacterium (e.g., C. diphtheriae-like strains), Kytococcus sedentarius (formerly Micrococcus sedentarius), Dermatophilus congolensis, and occasionally Staphylococcus species. These bacteria produce protease enzymes that break down keratin in the stratum corneum, forming characteristic pits measuring 0.5–7 mm in diameter.
A by-product of this degradation is the production of sulfur compounds, responsible for the foul, cheesy odour often described as intensely unpleasant. The bacteria thrive in warm, moist environments created by:
- Hyperhidrosis (excessive sweating of palms or soles).
- Occlusive footwear (e.g., rubber boots, closed shoes with poor ventilation).
- Prolonged occlusion and high skin pH, promoting bacterial proliferation.
- Poor hygiene, maceration from moisture, and friction on weight-bearing areas.
Unlike true infections, pitted keratolysis arises from the patient’s own skin flora under favourable conditions, not external pathogens. Risk factors include tropical climates, barefoot walking in moist soil, obesity, diabetes, immunosuppression, and inadequate foot drying.
Clinical Features
The hallmark of pitted keratolysis is multiple, discrete, punched-out pits on the soles of the feet, especially the balls, heels, and toes, often bilateral. These superficial erosions (1–7 mm diameter) may coalesce into larger eroded patches and become more prominent when wet. Key features include:
- White or greyish discoloration with macerated, wrinkly skin.
- Foul odour, exacerbated by sweating or occlusion, due to sulfur volatiles.
- Asymptomatic in most cases, but possible burning, itching, soreness, or pain on walking.
- Occasional green/brown hue around pits or slimy texture.
Symptoms intensify with moisture exposure, and pits may show raised, hyperkeratotic borders resembling rings (ringed keratolysis). Palmar lesions are rare but mirror foot presentation in high-risk occupations.
Variations in Skin Types
In lighter skin types, pits appear as white superficial depressions with clear crater outlines, often stark against normal skin. The surrounding skin may show maceration or erythema.
In darker skin types, lesions present as hyperpigmented or greyish pits with subtle borders, sometimes blending into surrounding hyperpigmentation; the odour remains prominent. Diagnosis may require dermoscopy to highlight pit walls in pigmented skin.
Complications
Pitted keratolysis is typically benign but can lead to secondary issues:
- Social embarrassment from persistent foot odour.
- Secondary infections if pits crack or macerate, allowing bacterial/fungal entry.
- Chronic hyperhidrosis exacerbation, leading to discomfort.
- Rarely, pain interfering with mobility in severe cases.
No systemic complications occur, but untreated cases in diabetics or immunocompromised individuals risk cellulitis.
Diagnosis
Diagnosis relies on clinical examination recognizing pits, odour, and history of hyperhidrosis/occlusive shoes. Dermoscopy reveals pit details and walls. A Wood’s lamp may show coral-red fluorescence if fluorescent bacteria (e.g., Corynebacterium) are present, though not always.
To exclude differentials:
- KOH preparation rules out tinea pedis (fungal hyphae absent).
- Culture confirms bacteria if needed, but rarely required.
- Biopsy unnecessary unless atypical.
Differential Diagnoses
| Condition | Key Distinguishing Features |
|---|---|
| Tinea pedis | Scaling, interdigital involvement, fungal elements on KOH; no pits/odour. |
| Erythrasma | Uniform brown patches, coral-red Wood’s lamp fluorescence; no pits. |
| Plantar warts | Hard, thrombosed capillaries, verrucous surface; HPV positive. |
| Hyperhidrosis alone | Maceration without pits/odour; no bacterial overgrowth. |
| Psoriasis | Thick plaques, nail changes, family history; biopsy confirmatory. |
Treatment
Treatment focuses on reducing moisture and bacterial load. Most cases resolve with hygiene.
General Measures
- Daily washing with antibacterial soap (e.g., chlorhexidine), thorough drying.
- Wear breathable footwear, cotton socks changed frequently; alternate shoes.
- Avoid occlusive shoes; use absorbent powders (e.g., talc).
Topical Therapies
- Topical antibiotics: Clindamycin, erythromycin, mupirocin lotion twice daily for 2–4 weeks.
- Benzoyl peroxide 5–10% gel/foam daily (antibacterial, drying).
- Combination with keratolytics (e.g., salicylic acid) for hyperkeratosis.
Systemic if Refractory
- Oral erythromycin or clindamycin for 2 weeks in severe/recurrent cases.
Hyperhidrosis Management
- Aluminium chloride 20% antiperspirant nightly.
- Iontophoresis or botulinum toxin for recalcitrant sweating.
Outcome
With adherence, pitted keratolysis resolves in 2–4 weeks; recurrence common without lifestyle changes. Prognosis excellent; no scarring. Patient education on prevention crucial.
Frequently Asked Questions (FAQs)
Q: Is pitted keratolysis contagious?
A: No, it results from overgrowth of normal skin bacteria, not person-to-person transmission.
Q: How can I prevent pitted keratolysis?
A: Keep feet dry, use breathable shoes/socks, practice good hygiene, and treat hyperhidrosis.
Q: Does pitted keratolysis cause pain?
A: Usually asymptomatic, but may cause burning/itching; pain rare unless complicated.
Q: Can it affect hands?
A: Rarely, mainly palms in occupations with moisture occlusion like farming.
Q: When should I see a doctor?
A: If odour/pits persist despite hygiene, or with pain/redness suggesting secondary infection.
References
- Pitted keratolysis — Wikipedia. 2023-10-15. https://en.wikipedia.org/wiki/Pitted_keratolysis
- Pitted Keratolysis: Symptoms, Treatment, and More — WebMD. 2024-01-12. https://www.webmd.com/skin-problems-and-treatments/what-is-pitted-keratolysis
- Pitted Keratolysis: What It Is, Causes & Treatment — Cleveland Clinic. 2023-08-22. https://my.clevelandclinic.org/health/diseases/23285-pitted-keratolysis
- Keratolysis, Pitted — Unbound Medicine (5-Minute Clinical Consult). 2024-05-01. https://www.unboundmedicine.com/5minute/view/5-Minute-Clinical-Consult/1688695/3.0/Keratolysis_Pitted
- Pitted keratolysis: an infective cause of foot odour — PMC – NIH (Indian J Dermatol). 2015-04-01. https://pmc.ncbi.nlm.nih.gov/articles/PMC4401600/
- Pitted Keratolysis — DermNet NZ. 2022-07-15. https://dermnetnz.org/topics/pitted-keratolysis



