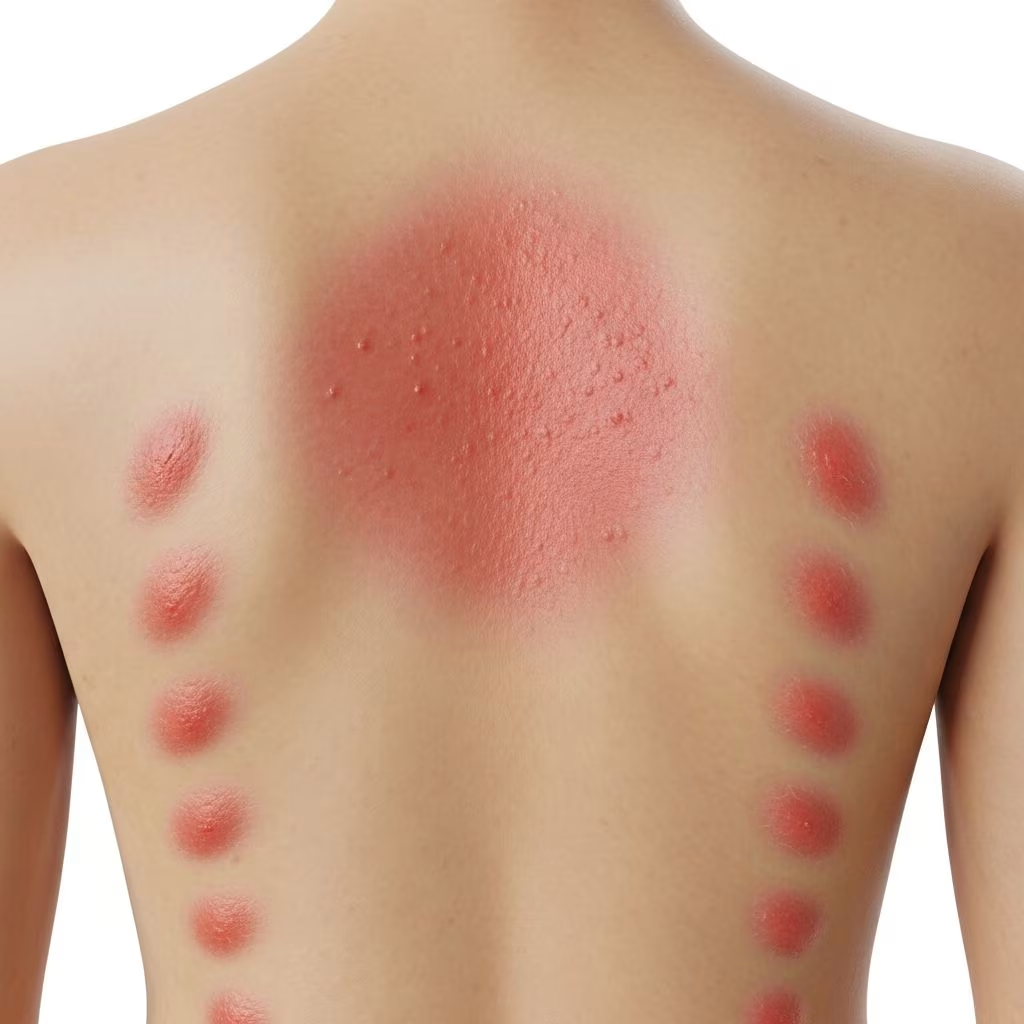
Pityriasis rosea is a benign, self-limiting skin condition characterized by distinctive oval, scaly patches that typically resolve within weeks to months without scarring. It commonly affects young adults and often follows a viral trigger, presenting as a widespread rash resembling a Christmas tree pattern on the trunk.
Recognizing the Signs of Pityriasis Rosea
The condition unfolds in distinct phases, beginning with a single large lesion known as the herald patch, followed by a more generalized eruption. Early detection through symptom awareness helps in distinguishing it from other dermatoses.
The Initial Herald Patch
Most cases start with the appearance of a solitary, salmon-colored plaque measuring 2 to 10 cm in diameter, often on the abdomen, chest, or back. This herald patch features a fine scale trailing its periphery, resembling a collarette, and emerges 1 to 2 weeks before the secondary rash. Mild itching may accompany it, though some individuals notice no discomfort.
Progression to the Full Rash
After the herald patch, smaller lesions—2 to 5 cm oval spots with similar scaling—erupt in crops, predominantly along skin tension lines on the trunk, creating a fir-tree configuration. The rash spares the face, palms, and soles, and may extend to proximal limbs in extensive cases. Itching intensifies for many, peaking in the second week.
- Duration: Total rash persists 6 to 12 weeks, with peak activity at 2 to 4 weeks.
- Associated symptoms: Fatigue, low-grade fever, sore throat, or mild malaise in up to 50% of patients preceding the rash.
- Rare oral involvement: Enanthems or white patches in mouth or throat resolve concurrently with skin lesions.
Potential Triggers and Underlying Causes
While the exact etiology remains elusive, strong evidence points to reactivation of human herpesviruses 6 and 7 (HHV-6/7), akin to roseola in children. Upper respiratory infections may precede onset, suggesting streptococcal or other microbial roles, though not proven causative.
| Possible Triggers | Description | Evidence Level |
|---|---|---|
| HHV-6/7 Reactivation | Detected in lesional skin and blood; antiviral response supports link | Strong |
| Medications | Drug-induced variants mimic PR, resolve on discontinuation (e.g., terbinafine) | Moderate |
| Seasonal Factors | Peaks in spring/autumn; UV exposure may influence | Observational |
Autoimmunity or atopy contributes rarely, but the condition is not contagious person-to-person.
Accurate Diagnosis: Key to Differentiation
Clinical pattern suffices for diagnosis in classic presentations, but biopsy confirms if atypical. Histology shows spongiosis, parakeratosis, and lymphocytic infiltrate in a pattern distinct from eczema or psoriasis.
Common Mimics and How to Distinguish
- Guttate psoriasis: Smaller drop-like lesions with thicker silvery scales; positive Auspitz sign.
- Tinea corporis: Annular with central clearing; KOH prep positive.
- Pityriasis lichenoides: Chronic relapsing papules with mica scales.
- Syphilis (secondary): Palmar/plantar involvement; RPR/FTA-ABS tests.
Special tests rarely needed unless persistent or in pregnancy.
Symptom Management Strategies
As pityriasis rosea self-resolves, treatment focuses on pruritus relief and accelerating clearance in severe cases. Watchful waiting suits mild presentations.
Topical and Supportive Care
Daily emollients restore barrier function and soothe. Calamine lotion or menthol/pramoxine preparations provide instant itch relief. Mid-potency corticosteroids like triamcinolone 0.1% ointment applied twice daily for 1-2 weeks reduce inflammation without significant atrophy risk.
- Cool oatmeal baths or compresses calm acute flares.
- Avoid irritants: Harsh soaps, hot showers, tight clothing.
Oral Medications for Moderate Itch
Sedating antihistamines (e.g., hydroxyzine 25mg nightly) excel for nocturnal symptoms. Short prednisone bursts (0.5mg/kg x 1 week) reserved for debilitating pruritus.
Advanced Interventions for Persistent Cases
Severe or prolonged rashes warrant targeted therapies backed by trials.
Antiviral Therapy: Acyclovir Efficacy
Acyclovir (400-800mg 5x/day x 7 days) hastens resolution in HHV-linked cases, with studies showing 70-90% improvement by week 2 vs. placebo. Ideal for early severe disease.
Phototherapy Options
Narrowband UVB (3-4x/week x 4 weeks) reduces rash severity and itch in 80% of patients. UVA1 for extensive involvement; requires dermatologist oversight to minimize pigmentation risks.
| Treatment | Dosage/Regimen | Efficacy Evidence | Side Effects |
|---|---|---|---|
| Acyclovir | 800mg PO 5x/day x7d | Significant resolution speedup (RCTs) | GI upset, rare nephrotoxicity |
| NB-UVB | 3x/wk x4wks | 70-80% improvement | Erythema, hyperpigmentation |
| Topical Steroid | q12h x1-2wks | Symptom relief (consensus) | Skin thinning (prolonged use) |
Macrolides like erythromycin lack benefit per larger trials.
Special Considerations: Pregnancy and Children
Pregnant individuals risk fetal loss if onset in first 15 weeks; prompt antiviral evaluation advised. In children, milder course; supportive care primary. Immunocompromised may experience atypical persistence.
Expected Timeline and Prognosis
90% resolve by 8 weeks; residual pigmentation fades over months. Recurrence rare (2%). No long-term sequelae.
Frequently Asked Questions (FAQs)
Is pityriasis rosea contagious?
No, despite viral associations, it does not spread person-to-person.
How long does the rash last?
Typically 6-12 weeks; treatments can shorten to 2-4 weeks.
Can I exercise or swim with pityriasis rosea?
Yes, but use emollients post-activity; avoid pools if open skin to prevent irritation.
Does pityriasis rosea leave scars?
Rarely; post-inflammatory hyper/hypopigmentation resolves gradually.
When should I see a dermatologist?
If pregnant, rash >3 months, severe itch disrupting life, or atypical features.
Living Comfortably During an Outbreak
Maintain gentle skincare: Fragrance-free cleansers, lukewarm showers, cotton clothing. Stress reduction via mindfulness aids as flares link to immune shifts. Track symptoms with photos for provider consults.
Nutritional support with omega-3s and vitamin D may bolster skin repair, though unproven specifically for PR.
References
- Pityriasis Rosea: Diagnosis and Treatment — American Academy of Family Physicians. 2018-01-01. https://www.aafp.org/pubs/afp/issues/2018/0101/p38.html
- Pityriasis rosea: Diagnosis and treatment — American Academy of Dermatology. 2023. https://www.aad.org/public/diseases/a-z/pityriasis-rosea-treatment
- Pityriasis Rosea Rash: Symptoms, Causes, & Treatment — WebMD. 2024. https://www.webmd.com/skin-problems-and-treatments/whats-pityriasis-rosea
- Pityriasis Rosea — NCBI StatPearls. 2023-07-17. https://www.ncbi.nlm.nih.gov/books/NBK448091/
- Pityriasis Rosea — St. Louis Children’s Hospital. 2024. https://www.stlouischildrens.org/conditions-treatments/pityriasis-rosea
- Pityriasis rosea — NHS UK. 2023. https://www.nhs.uk/conditions/pityriasis-rosea/
- Pityriasis Rosea (Christmas Tree Rash): Causes & Treatment — Cleveland Clinic. 2023-09-28. https://my.clevelandclinic.org/health/diseases/17729-pityriasis-rosea