
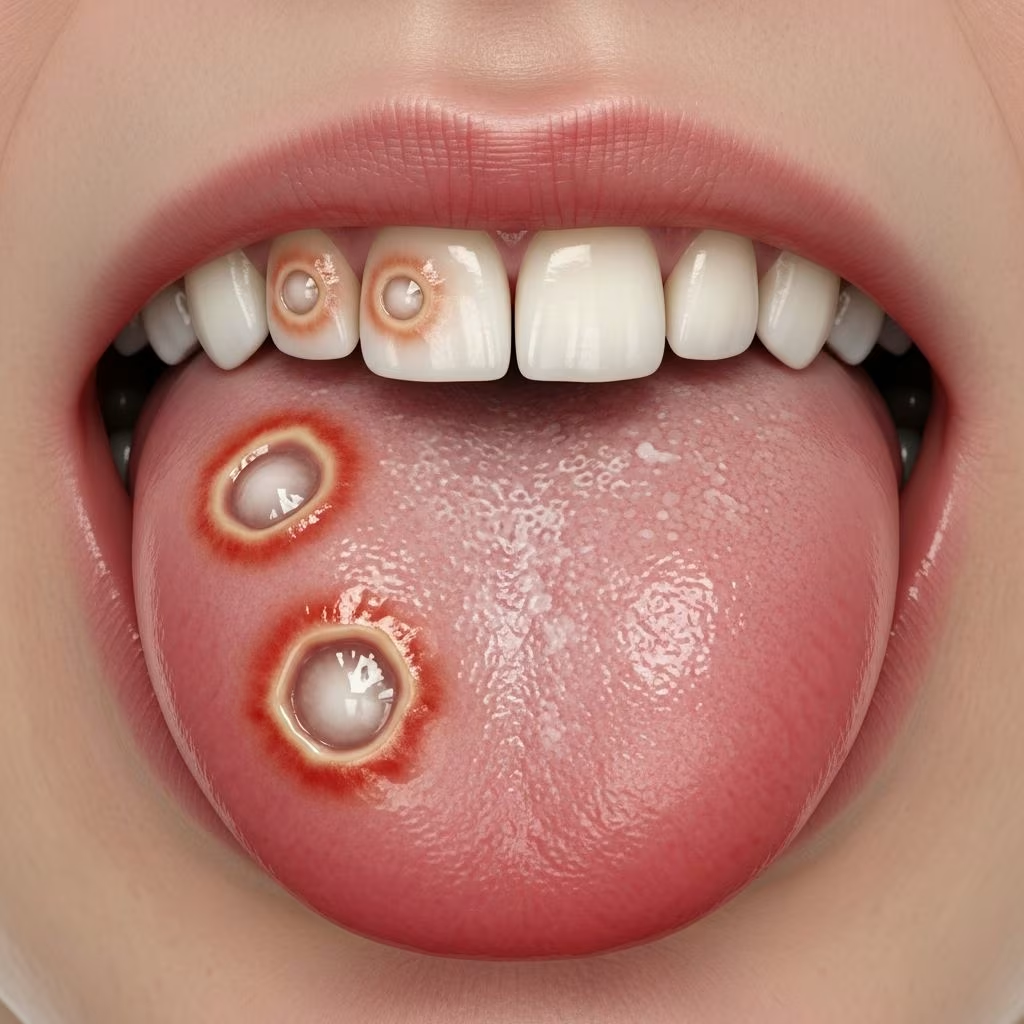
Authoritative facts about stomatitis: What it looks like and differential diagnosis (list), cause and pathogenesis of stomatitis, making the diagnosis, management (including prevention of stomatitis), and recurrent aphthous stomatitis (RAS).
What is stomatitis?
Stomatitis refers to inflammation of the oral mucosa, the lining of the mouth, encompassing a range of conditions from mild redness and swelling to painful ulcers that disrupt daily activities like eating and speaking. This broad term covers acute and chronic forms, often presenting as discrete ulcers, swelling, or whitish lesions, and can lead to secondary infections in vulnerable patients.
Commonly affecting the cheeks, gums, tongue, lips, and palate, stomatitis impairs quality of life, causing pain, burning sensations, and sometimes dehydration due to reduced intake. It may be primary or secondary to systemic diseases, infections, irritants, or nutritional deficiencies.
Who gets stomatitis?
Stomatitis affects individuals across all ages, with higher prevalence in children for recurrent forms like aphthous stomatitis (up to 40% of recurrent ulcers) and adults experiencing drug-induced or stress-related episodes. Risk factors include immunosuppression, poor oral hygiene, ill-fitting dentures, vitamin deficiencies (e.g., B12, iron), and autoimmune conditions. Children with periodic fever syndromes like PFAPA are particularly prone to recurrent episodes.
What causes stomatitis?
Stomatitis arises from diverse etiologies, categorized as infectious, traumatic, chemical, allergic, or systemic. Viral causes like herpes simplex virus (HSV-1) lead to herpetic stomatitis with clustered vesicles. Bacterial infections, such as acute necrotizing ulcerative gingivitis, produce punched-out ulcers, while fungal overgrowth (e.g., candidiasis) causes whitish patches in denture wearers.
Non-infectious triggers include mechanical irritation from sharp teeth or dentures, chemical exposure to spicy foods or tobacco, and medications like NSAIDs, sulfonamides, or chemotherapy agents inducing fixed drug eruptions or Stevens-Johnson syndrome (SJS). Nutritional deficiencies, stress, hormonal changes, and genetic predispositions contribute to idiopathic recurrent aphthous stomatitis (RAS).
Systemic associations link stomatitis to inflammatory bowel disease, Behcet’s syndrome, cyclic neutropenia, and hyperimmunoglobulin D syndrome (HIDS), where aphthous-like ulcers recur with fever and lymphadenopathy.
What are the clinical features of stomatitis?
Symptoms vary by type but commonly include redness, swelling, burning pain, ulcers, and halitosis. Aphthous ulcers appear as round, shallow lesions with a yellow-gray membrane and erythematous halo, lasting 5-14 days without scarring in minor forms.
- Pain: Especially during eating acidic/spicy foods; hinders nutrition.
- Ulcers: Single or multiple, 1-10mm; major forms >10mm, deeper, scar.
- Associated signs: Fever (herpetic, SJS), lymphadenopathy, dry mouth, bleeding.
- Herpetiform: Numerous tiny ulcers coalescing into larger areas.
Severe variants like noma involve necrotic tissue destruction in malnourished patients.
Differential diagnosis
| Condition | Key Features | Differentiator |
|---|---|---|
| Recurrent Aphthous Stomatitis (RAS) | Painful, recurrent ulcers; no vesicles; non-vesicular | Idiopathic; excludes systemic causes |
| Herpetic Stomatitis | Clustered vesicles on keratinized mucosa; fever | Viral culture/PCR positive |
| Denture Stomatitis | Redness under dentures; fungal | Associated with poor hygiene |
| Stevens-Johnson Syndrome | Mucosal erosions, skin blisters, systemic symptoms | Drug history; Nikolsky sign |
| Behçet’s Disease | Genital/oral ulcers, uveitis | Systemic vasculitis |
| Cyclic Neutropenia | Ulcers every 21 days with neutropenia | ELANE mutation; CBC |
Pathogenesis
The underlying mechanisms involve immune dysregulation, with T-cell mediated cytotoxicity in RAS targeting oral epithelium. In infectious forms, pathogens trigger epithelial damage. Systemic diseases like autoinflammatory syndromes (PFAPA, HIDS) involve cytokine storms and neutrophil activation, leading to mucosal ulceration. Trauma breaches the mucosal barrier, exposing antigens and provoking inflammation.
Making the diagnosis
Diagnosis relies on clinical history, examination, and exclusion of mimics. Assess ulcer morphology, recurrence pattern, systemic symptoms, and triggers. Biopsy rules out malignancy or pemphigus (immunofluorescence shows IgG/C3 deposition). Labs include CBC for neutropenia, nutritional panels, viral serology, and swabs for infections.
For recurrent cases, review for PFAPA (periodic fevers, aphthae, pharyngitis, adenitis) or drug reactions.
Management of stomatitis
General measures
- Avoid irritants: Spicy/acidic foods, tobacco, alcohol.
- Oral hygiene: Soft toothbrush, antiseptic rinses (chlorhexidine).
- Pain relief: Topical anesthetics (lidocaine), analgesics.
- Diet: Soft, bland foods; hydration.
Specific treatments
Topical therapies (first-line for mild/RAS): Corticosteroids (triamcinolone paste), antimicrobials (tetracycline rinse), silver nitrate cauterization.
Systemic for severe/recalcitrant: Corticosteroids, colchicine, thalidomide, immunosuppressants. For infections: Acyclovir (HSV), antifungals (nystatin).
Denture stomatitis: Improved fit, antifungals. SJS: ICU supportive care.
Prevention
- Address deficiencies: Vitamin B12, folate, iron supplementation.
- Stress management, nicotine replacement if quitting.
- Regular dental checks for trauma sources.
Recurrent aphthous stomatitis (RAS)
RAS, the most common oral ulcerative condition (25% adults, 40% children), features recurrent, self-limited ulcers without identifiable cause after excluding differentials. Subtypes:
| Subtype | Prevalence | Size | Number | Duration | Scarring |
|---|---|---|---|---|---|
| Minor | >70% | 3-10mm | 1-5 | 7-10 days | No |
| Major | 10% | >10mm | Few | Weeks | Yes |
| Herpetiform | 10% | <1mm | 10-100 | 1-2 weeks | Rare |
Triggers: Stress, trauma, allergies. Management escalates from topicals to systemic (e.g., steroids, dapsone).
Frequently asked questions (FAQs) in stomatitis
Q. How long does stomatitis last?
A. Most cases resolve in 1-2 weeks with supportive care; RAS minor ulcers heal in 7-10 days, major in weeks.
Q. Are canker sores contagious?
A. No, unlike cold sores (HSV); aphthous ulcers are non-infectious.
Q. When should I see a doctor for mouth ulcers?
A. If ulcers persist >2 weeks, recur frequently, accompany fever/systemic symptoms, or exceed 1cm.
Q. Can stress cause stomatitis?
A. Yes, stress triggers RAS outbreaks via immune modulation.
Q. Is stomatitis a sign of cancer?
A. Rarely; persistent, indurated ulcers warrant biopsy to exclude malignancy.
References
- Recurrent Aphthous Stomatitis: A Review — Brocklehurst P, et al. PMC – PubMed Central. 2015-04-07. https://pmc.ncbi.nlm.nih.gov/articles/PMC5367879/
- Stomatitis – Dental Disorders — Merck Manual Professional Edition. 2024. https://www.merckmanuals.com/professional/dental-disorders/symptoms-of-dental-and-oral-disorders/stomatitis
- Stomatitis | Overjet Dental Glossary — Overjet. 2024. https://www.overjet.com/glossary/stomatitis
- Stomatitis: What helps with inflammation of the oral mucosa? — Curaprox. 2023. https://curaprox.us/blog/post/stomatitis-what-helps-with-inflammation-of-the-oral-mucosa
- Stomatitis: Types, Symptoms, Causes, and Treatment — WebMD. 2024. https://www.webmd.com/oral-health/stomatitis-causes-treatment
- Aphthous Stomatitis — Children’s Hospital of Philadelphia (CHOP). 2024. https://www.chop.edu/conditions-diseases/aphthous-stomatitis



