
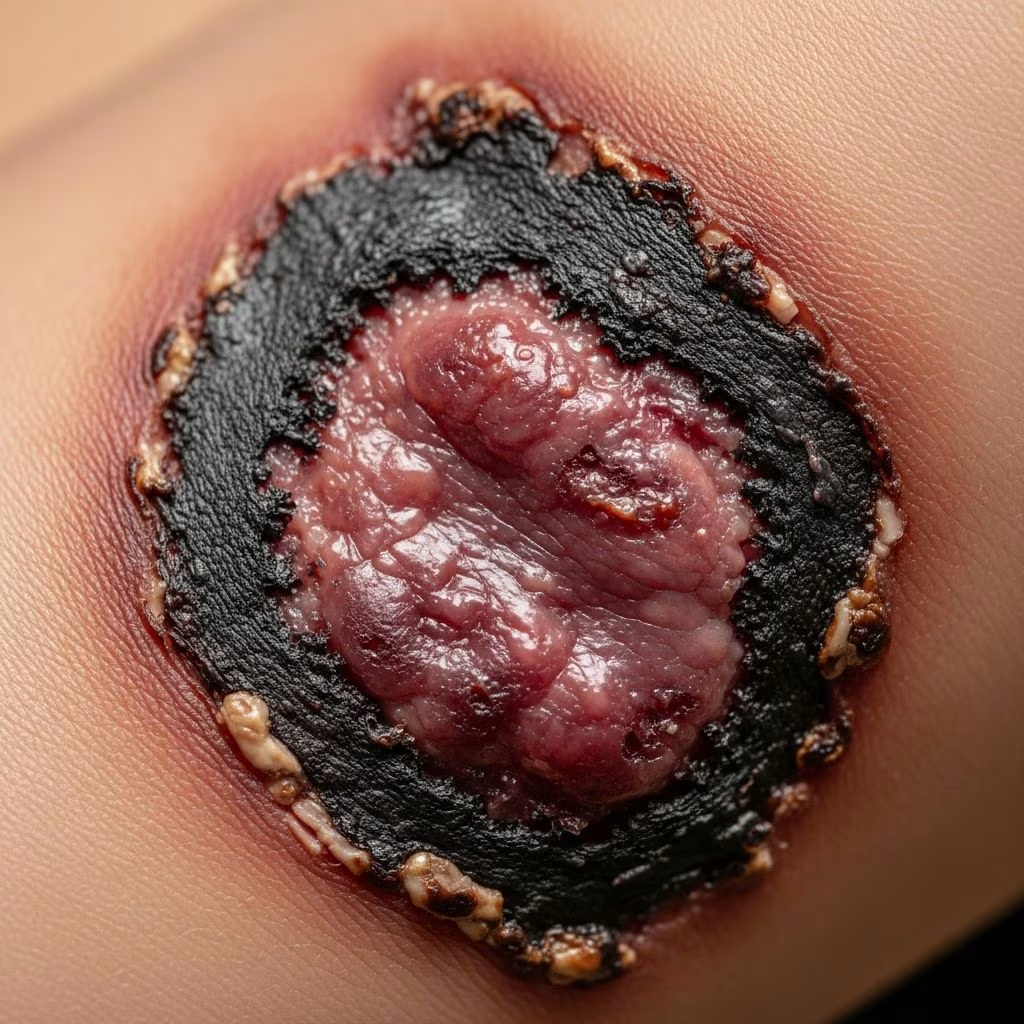
A thermal burn is a skin injury caused by any external heat source, such as naked flames from open fireplaces, house fires, hot liquids, steam, or hot surfaces. These burns affect the skin layers and can range from minor superficial damage to life-threatening full-thickness injuries. Understanding the classification, symptoms, and management is crucial for optimal outcomes.
What is a Thermal Burn?
Thermal burns result from excessive heat exposure, typically from contact with flames, scalding liquids, steam, or hot objects. Unlike chemical or electrical burns, thermal burns are purely heat-related. They account for a significant portion of burn injuries, with home incidents comprising about 25% of serious cases. Most are minor and managed outpatient, but severe burns (affecting over 10-20% total body surface area, TBSA) require specialized care.
The severity depends on heat intensity, duration of contact, and patient factors like age or comorbidities. Children and elderly are at higher risk due to thinner skin and reduced mobility.
Who Gets Thermal Burns?
Anyone can suffer a thermal burn, but certain groups are vulnerable:
- Children: Often from scalds with hot liquids or taps.
- Elderly: Due to mobility issues and thin skin.
- Individuals with disabilities: Limited ability to escape heat sources.
- Occupational exposure: Cooks, firefighters, welders.
Suspect non-accidental injury in children or elderly with unexplained burns, especially on feet, buttocks, or immersion patterns.
Classification of Thermal Burns
Burns are classified by depth (thickness) rather than traditional first/second/third-degree terms for better clinical accuracy:
| Depth | Alternative Name | Affected Layers | Appearance | Sensation | Healing Time |
|---|---|---|---|---|---|
| Superficial | First-degree | Epidermis only | Warm, painful, red, dry, blanches | Painful | 3-7 days |
| Partial thickness (superficial) | Second-degree superficial | Superficial dermis | Painful, red, blistered, moist, blanches | Very painful | 7-21 days |
| Partial thickness (deep) | Second-degree deep | Deep dermis | Paler, less blanching, mottled | Less painful | 3-8 weeks, may scar |
| Full thickness | Third-degree | Full dermis to subcutaneous | White, charred, leathery, insensate | Painless | Does not heal; requires grafting |
| Fourth-degree | – | Muscle, tendon, bone | Blackened, dry | Painless | Surgical intervention |
Superficial burns like sunburns preserve skin function. Deeper burns disrupt barrier, thermoregulation, and sensation.
Extent of Burn
Assess percentage of TBSA using Rule of Nines or Lund-Browder chart (more accurate for children):
- Adult head = 9%, each arm = 9%, each leg = 18%, front/back torso = 18% each, genitals = 1%.
Severity criteria:
- Minor: <10% TBSA partial in adults, <5% full-thickness.
- Moderate: 10-20% partial or 2-10% full-thickness; admit but not always burn center.
- Major: >20-25% partial, >10% full-thickness, or involving face/hands/genitals/joints.
Signs and Symptoms
Symptoms vary by depth:
- Superficial: Erythema, pain, no blisters (e.g., sunburn).
- Partial superficial: Blisters, severe pain, wet/moist.
- Partial deep: Thicker blisters, pale, reduced pain.
- Full thickness: Dry, leathery, painless due to nerve destruction.
Systemic: Hypovolemia, shock in large burns; hypermetabolism later.
Complications
Burns predispose to:
- Infection: Cellulitis, burn wound infection (Pseudomonas), sepsis.
- Fluid loss: Leading to hypovolemic shock.
- Respiratory issues: Inhalation injury from smoke.
- Scarring/contractures: Hypertrophic scars, keloids.
- Systemic: Hypermetabolism, organ failure in major burns.
Assessment
Follow ABCDE: Airway, Breathing, Circulation, Disability, Exposure. Stabilize before wound assessment. Check for inhalation (soot in mouth, hoarseness), associated trauma, comorbidities.
Management
Pre-hospital / First Aid
- Stop burning process: Remove from heat, extinguish flames (stop-drop-roll), remove hot clothing/jewelry.
- Cool burn: 20 minutes cool running water (10-15°C); avoid ice. For large burns (>10% TBSA), warm patient to prevent hypothermia.
- Cover: Loose sterile dressing; no ointments initially.
- Pain relief: Paracetamol/ibuprofen.
- Seek help: For large/deep burns, face/hands/genitals, or vulnerable patients.
Hospital Management
Fluid resuscitation (Parkland formula: 4ml/kg/%TBSA lactated Ringer’s, half in first 8h). Tetanus prophylaxis, analgesia, NG tube if ileus.
Wound Care
Outpatient Strategies
- Clean with saline; debride blisters >2cm or loose.
- Moist dressings: Non-adherent (e.g., silicone), hydrogels, silver-impregnated for infection risk.
- Change every 3-7 days; elevate limb.
- Review 48h post-injury.
Inpatient Strategies
- Daily cleaning, topical antimicrobials: Silver sulfadiazine 1%, silver nitrate, mafenide.
- Biologic dressings (e.g., Biobrane), excision/grafting for deep burns.
- Nutrition: Early enteral, Curreri formula (25kcal/kg + 40kcal/%TBSA).
Topical Antibacterials
Common agents:
- Silver sulfadiazine 1%: Broad-spectrum, painless, leukopenia risk.
- Silver nitrate 0.5%: Stains, hypotonic.
- Mafenide 10%: Penetrates eschar, acidic pain.
Avoid in pregnancy/sulfa allergy.
Referral Criteria
- >10% TBSA partial/full in adults; >5% children.
- Face, hands, feet, genitals, joints.
- Inhalation injury, comorbidities.
Prevention
- Safe hot water (<49°C), guards on heaters.
- Smoke alarms, fire extinguishers.
- Educate on ointment fire risks: Paraffin-based creams increase flammability; use less greasy alternatives.
Frequently Asked Questions (FAQs)
Q: How long should I cool a burn?
A: Cool small burns with running water for 20 minutes. Avoid prolonged cooling in large burns to prevent hypothermia.
Q: When to seek emergency care?
A: For burns > thumb size in children, any full-thickness, or involving critical areas.
Q: Do I pop blisters?
A: No; intact blisters protect. Debride only large/broken ones.
Q: What about ointments causing burns?
A: Paraffin-based increase fire risk; inform patients and suggest safer emollients.
Q: How to estimate burn size?
A: Use palm (0.8% TBSA adult) or Rule of Nines.
References
- Thermal Burns – StatPearls — NCBI Bookshelf. 2025-01. https://www.ncbi.nlm.nih.gov/books/NBK430773/
- Thermal burns – assessment and acute management — RACGP. 2012-06. https://www.racgp.org.au/afp/2012/june/thermal-burns-assessment-and-acute-management
- Thermal burns — DermNet NZ. Accessed 2026. https://dermnetnz.org/topics/thermal-burn
- Thermal burns associated with the use of ointments — DermNet NZ. Accessed 2026. https://dermnetnz.org/topics/burns-from-ointments



