
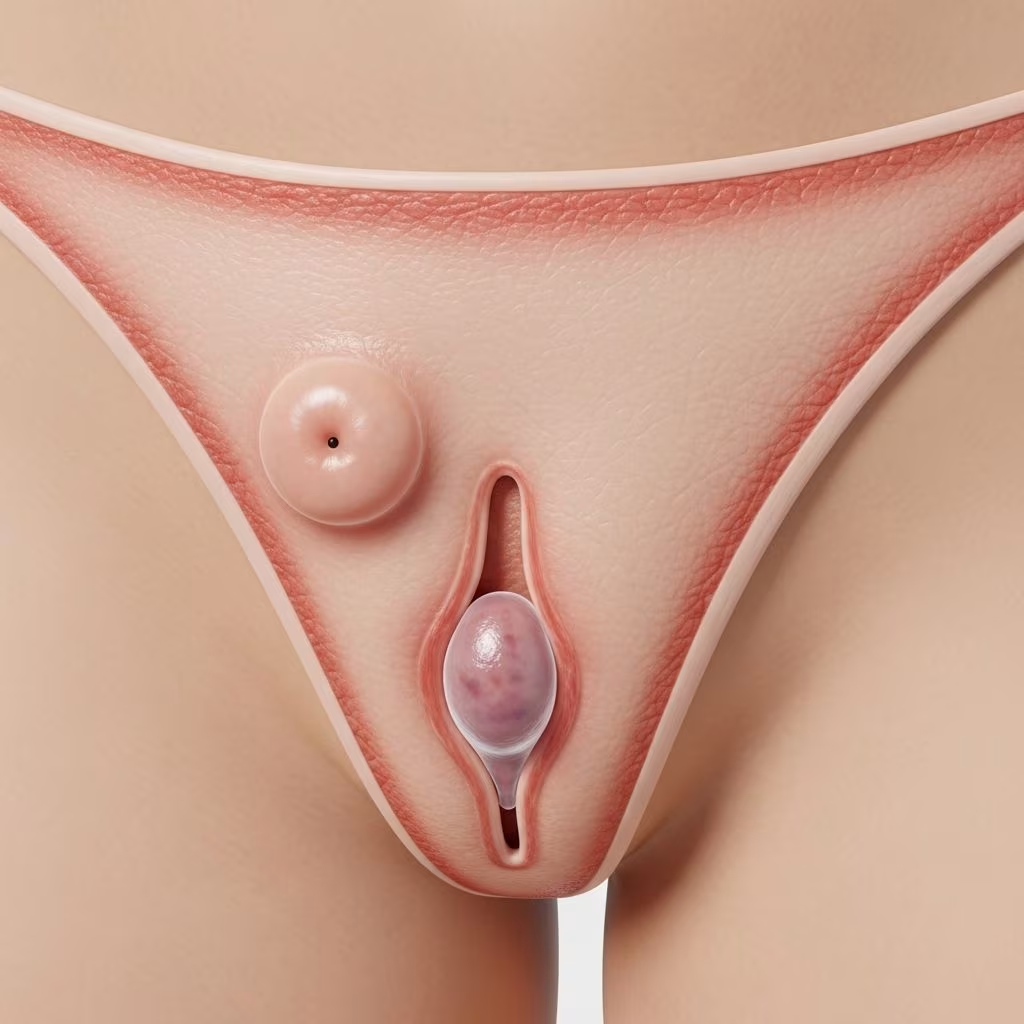
A vulval cyst is an encapsulated lesion containing fluid or semi-fluid material on the external female genitalia. These cysts arise from various structures in the vulvar region and can affect females of any age, though specific types predominate in certain groups.
Introduction
The vulva comprises complex anatomy including the labia majora, labia minora, clitoris, vaginal introitus, Bartholin glands, Skene glands, and minor vestibular glands. Cysts develop from these when ducts obstruct or tissues trap material. They are often benign, dome-shaped, firm or fluctuant, and may be asymptomatic or cause pain, dyspareunia (painful intercourse), or cyclic discomfort depending on location and inflammation.
While many cysts are incidental findings, others present due to infection, trauma, or growth. Early recognition aids management, as most resolve without intervention, but complications like abscesses require prompt care.
Demographics
Vulval cysts occur across all ages:
- Neonates: Skene duct cysts from maternal estrogen effects.
- Puberty to 40s: Vestibular mucinous cysts from minor vestibular glands.
- Middle-aged/elderly: Epidermoid cysts on labia majora; milia on labia.
- Adults (2% lifetime risk): Bartholin duct cysts.
- Childhood (by age 5): Canal of Nuck cysts.
Prevalence varies; Bartholin cysts affect about 2% of adult women. Rare types like steatocystoma or eruptive vellus hair cysts have no strong age bias but are sporadic.
Causes
Vulval cysts result from:
- Developmental anomalies: Incomplete regression, e.g., canal of Nuck (hydrocele equivalent), Gartner (mesonephric duct remnant).
- Genetic: Autosomal dominant steatocystoma from pilosebaceous duct proliferation.
- Post-traumatic/surgical: Epidermoid (inclusion) cysts from trapped epithelium; cutaneous endometriosis from obstetric trauma.
- Spontaneous/obstruction: Gland duct blockage (Bartholin, Skene, vestibular); ingrown hairs (pilonidal-like).
Mucinous cysts stem from minor vestibular glands along Hart lines on inner labia minora. Pilonidal disease on vulva mimics intertrigo from ingrown hairs near clitoris.
Clinical Features
Cysts present as discrete, dome-shaped lumps varying by type:
| Type | Location | Appearance/Size | Symptoms |
|---|---|---|---|
| Vulval milia | Labia (older women) | 1–2 mm white cysts, multiple | Asymptomatic, incidental |
| Epidermoid | Labia majora (cutaneous) | Solitary/multiple, <1 cm; giant rare | Painless lump; post-surgical |
| Bartholin/Skene | 4/8 o’clock introitus; distal urethra | Mucoid fluid; lump or abscess | Pain if infected |
| Mucinous (vestibular) | Inner labia minora (Hart lines) | Palpable lump | Pain if inflamed |
| Canal of Nuck | Inguinal/labium majus | Skin-coloured swelling | Asymptomatic, hernia-like |
| Gartner | Anterolateral vaginal wall | Small unilateral, interlabial mass | Late adolescence |
| Eruptive vellus hair | Labia majora (rare) | Yellow-brown papules | Multiple |
| Steatocystoma | Vulva (rare) | Papules with oily fluid | Late-onset |
| Pilonidal | Near clitoris | Papule/nodule | Painless |
| Cutaneous endometriosis | Trauma sites | Nodules/cysts with blood | Cyclic pain |
Symptoms include pain, swelling, dyspareunia (cyclic in endometriosis), or infection signs (redness, pus). Location aids identification: posterior for Bartholin, anterior for Skene/Gartner.
Complications
Most cysts are benign, but complications include:
- Infection/abscess: Common in Bartholin/Skene; requires drainage/antibiotics.
- Rupture/inflammation: Pain, discharge.
- Dyspareunia/urinary issues: Large cysts.
- Recurrence: Post-treatment, especially Bartholin.
- Rare associations: Gartner cysts with renal anomalies; endometriomas with cyclic bleeding.
Infected cysts cause tender swelling; untreated abscesses lead to fistula or sepsis (rare).
Diagnosis
Primarily clinical, based on age, site, appearance:
- History: Onset, trauma, symptoms, cycles.
- Exam: Visual/palpation; speculum if vaginal.
- Imaging: Ultrasound for deep/inguinal cysts (e.g., Nuck, Gartner).
- Biopsy: Persistent, atypical, or suspicious (e.g., solid, ulcerated).
No routine labs; culture pus if infected. Differentiate from malignancy via excision histology if needed.
Differential Diagnoses
Consider:
- Infectious: Folliculitis, abscess, hidradenitis.
- Inflammatory: Lichen sclerosus, psoriasis, contact dermatitis (itchy, white patches).
- Neoplastic: Vulvar cancer, Paget disease, DFSP (rare, persistent masses).
- Other cysts/lumps: Fordyce spots, sebaceous cysts, lipomas.
- Vascular: Angiokeratomas, haemangiomas.
Biopsy atypical lesions; cancer risk low but higher in lichen sclerosus.
Treatment
Many asymptomatic cysts need no treatment. Options:
- Conservative: Observation; warm sitz baths (soften/drain).
- Drainage: Needle aspiration (recurs); incision for abscess.
- Marsupialisation: Bartholin cysts (creates pouch).
- Excision: Symptomatic/recurrent; full for epidermoid/endometriosis.
- Antibiotics: Infected (e.g., cephalexin).
- Other: Cryotherapy/shave for small; avoid tight clothes, use cotton underwear.
Surgery under local/general; post-op care prevents recurrence.
Outcome
Excellent for most; benign with low recurrence if fully excised. Bartholin cysts recur in 10-20% post-marsupialisation. Monitor for infection/malignancy in persistent cases. Patient education on hygiene reduces complications.
Frequently Asked Questions (FAQs)
What is a vulval cyst?
An encapsulated fluid-filled lump on the vulva, often benign from gland obstruction or development.
Do vulval cysts need treatment?
No, if asymptomatic; treat if painful/infected via drainage or excision.
How common are Bartholin cysts?
Affect 2% of adult women lifetime.
Can vulval cysts be cancerous?
Rarely; biopsy persistent/suspicious lumps.
What home care helps?
Sitz baths, loose cotton clothing, avoid irritants.
References
- Vulval Cysts — DermNet NZ. 2023. https://dermnetnz.org/topics/vulval-cysts
- Vaginal Lumps and Bumps: Causes and When to See a Doctor — Healthline. 2023-10-12. https://www.healthline.com/health/womens-health/vaginal-lumps-bumps
- Vulvovaginal Health in Post-Menopausal Women — bpac.org.nz. 2014-09. https://bpac.org.nz/bpj/2014/september/vulvovaginal.aspx
- Vulvar Dermatofibrosarcoma Protuberans in a 55-Year-Old Female — NIH/PMC. 2025. https://pmc.ncbi.nlm.nih.gov/articles/PMC12816800/



