
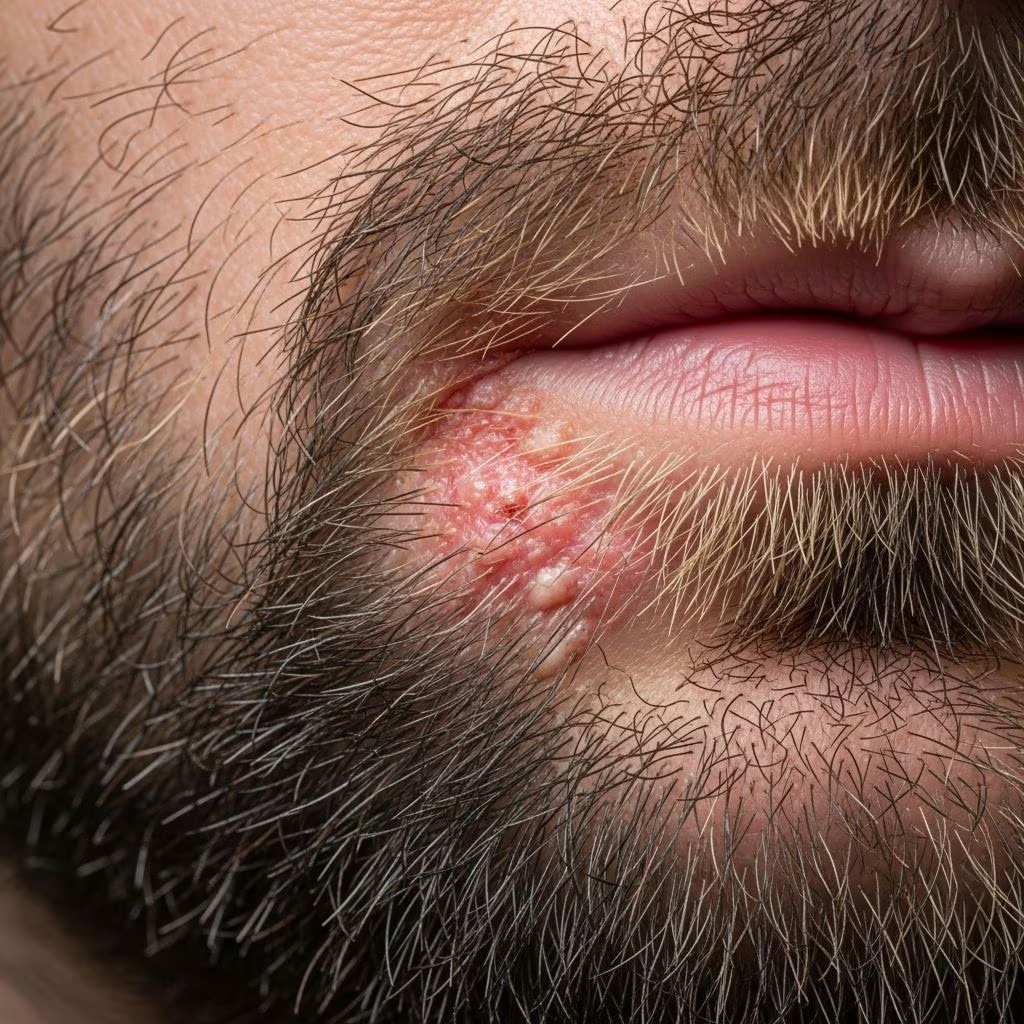
Tinea barbae is a fungal infection of the beard area caused by dermatophytes. It is also known as barber’s itch or ringworm of the beard. This condition primarily affects the skin, hair follicles, and hair shafts in the bearded region of males. Tinea barbae is relatively rare compared to other superficial fungal infections but can lead to significant discomfort, scarring, and occupational implications, particularly among individuals with animal exposure such as farmers and livestock handlers.
The infection is characterized by two main clinical variants: superficial noninflammatory type resembling tinea corporis and deep inflammatory type (tinea barbae profunda or kerion), which is more common and severe. Prompt diagnosis and treatment are crucial to prevent permanent hair loss, scarring, and secondary bacterial infections. Oral antifungal therapy is the cornerstone of management, with terbinafine and azoles like itraconazole being first-line agents.
What is tinea barbae?
Tinea barbae refers to a dermatophyte infection specifically involving the coarse terminal hairs of the beard and mustache area on the face and upper neck. Dermatophytes are keratinophilic fungi that thrive on skin, hair, and nails. Unlike tinea faciei, which affects glabrous (non-hairy) facial skin, tinea barbae invades hair follicles, leading to unique presentations involving hair breakage and follicular inflammation.
Historically termed ‘barber’s itch,’ it was associated with shared razors in barbershops, though modern hygiene has reduced this risk. Today, zoonotic transmission from animals predominates. The condition is ectothrix in pattern, where fungal spores coat the exterior of the hair shaft, causing easy fracturing. If untreated, it can result in cicatricial alopecia (scarring hair loss) and psychological distress due to visible facial disfigurement.
Who gets tinea barbae?
Tinea barbae predominantly affects adult males with facial hair, particularly those in agricultural occupations. High-risk groups include:
- Cattle farmers and dairy workers due to contact with infected cows (e.g., Trichophyton verrucosum).
- Individuals handling pets like dogs, cats, or horses carrying zoophilic dermatophytes such as Trichophyton mentagrophytes or Arthroderma benhamiae.
- Immunocompromised patients, including those on corticosteroids or with diabetes, who may experience more severe or disseminated disease.
- Rarely, barbers or clients from unhygienic shaving practices.
Children and women are rarely affected as they typically lack coarse facial hair. Occupational exposure accounts for most cases, with outbreaks reported in farming communities.
Causes of tinea barbae
Tinea barbae is caused by zoophilic dermatophytes, which are adapted to animal hosts but can infect humans. Common causative organisms include:
- Trichophyton verrucosum – from cattle, causing inflammatory kerion-like lesions.
- Trichophyton mentagrophytes (including zoophilic strains like T. mentagrophytes var. quinckeanum) – from rodents, horses, or dogs.
- Trichophyton erinacei or Arthroderma benhamiae – from hedgehogs or pets.
- Rarely, anthropophilic fungi like Trichophyton rubrum for superficial types, or Microsporum nanum.
Infection occurs via direct contact with infected animals, fomites (e.g., grooming tools), or soil. Fungal arthroconidia penetrate hair follicles, eliciting an immune response. Virulence factors include keratinases, proteases, and immunomodulators that facilitate invasion and inflammation.
Signs and symptoms of tinea barbae
Clinical presentation varies by type and causative fungus.
Superficial (sycosiform) tinea barbae
This rarer form mimics bacterial folliculitis or tinea corporis:
- Erythematous annular plaques with raised, scaly borders.
- Follicular papules, vesicles, or pustules.
- Hair breakage at the ostium (follicular opening) or easy epilation.
- Mild itching or burning; chronic if untreated.
Deep inflammatory (kerion) tinea barbae
More common, zoophilic-induced:
- Boggy, indurated plaques or nodules with oozing pustules.
- Yellow crusting, pain, and tenderness.
- Marked hair loss with ‘black dots’ (broken hairs).
- Regional lymphadenopathy, fever, malaise in severe cases.
- Potential scarring if delayed treatment.
An id reaction (autoeczematization) may occur post-treatment, presenting as widespread itchy papules due to circulating fungal antigens.
Diagnosis of tinea barbae
Diagnosis combines clinical suspicion with mycological confirmation:
- Clinical examination: History of animal contact, lesion morphology.
- Microscopy: KOH prep of plucked hairs/scrapings shows ectothrix spores, hyphae (gold standard).
- Culture: Sabouraud agar identifies species (2-3 weeks).
- Wood lamp: Dull green fluorescence with Microsporum spp.
- Biopsy: Rarely needed; shows granulomatous folliculitis, suppurative inflammation, fungal elements on PAS stain.
Differential includes bacterial sycosis (Staph aureus), pseudofolliculitis barbae, herpes zoster, or contact dermatitis. Culture distinguishes fungal from bacterial causes.
Treatment of tinea barbae
Oral antifungals are essential due to follicular involvement; topicals alone suffice only for very mild superficial cases.
Oral antifungals
| Agent | Dose | Duration | Notes |
|---|---|---|---|
| Terbinafine | 250 mg daily | 4-6 weeks | First-line; excellent efficacy against zoophilic spp. |
| Itraconazole | 200 mg daily | 4-6 weeks | Alternative; pulse dosing possible. |
| Fluconazole | 150-400 mg weekly | 6-8 weeks | For refractory cases. |
| Griseofulvin (micronized) | 500-1000 mg daily | 6-12 weeks | Less favored due to side effects, resistance. |
Continue 2 weeks post-clearance. Monitor LFTs for hepatotoxicity. Adjunct: topical azoles/allylamines for 4 weeks; keratolytics for crusts; short-course steroids for severe inflammation.
What is the prognosis for tinea barbae?
With prompt oral therapy, resolution occurs in 4-6 weeks without sequelae. Delayed treatment risks scarring alopecia, permanent hair loss, and secondary impetiginization. Recurrence is low if animal source is eliminated. Id reactions self-resolve.
Prevention of tinea barbae
- Avoid direct contact with potentially infected animals; use gloves.
- Veterinary check of livestock/pets; treat animal ringworm.
- Personal hygiene: clean razors, avoid sharing grooming tools.
- Protective clothing for farmers.
- Early treatment of superficial tinea elsewhere.
Related topics
- Tinea capitis
- Tinea corporis
- Tinea faciei
- Dermatophyte infections of the beard area
Frequently asked questions
Is tinea barbae contagious?
Yes, via direct contact or fomites, but human-to-human spread is rare; mainly zoonotic.
Can tinea barbae cause permanent hair loss?
Yes, if the kerion variant scars; early treatment prevents this.
How long does treatment take?
Typically 4-6 weeks of oral antifungals.
Can I shave with tinea barbae?
Avoid until treated; use disposable razors if necessary.
Does tinea barbae affect women?
Rarely, only if facial hair present.
References
- Tinea Barbae – StatPearls — Pradeep Kumar M et al. NCBI Bookshelf. 2023-08-07. https://www.ncbi.nlm.nih.gov/books/NBK563204/
- Tinea barbae (fungal infection of the beard) — DermNet NZ. 2023. https://dermnetnz.org/topics/tinea-barbae
- Tinea Barbae (Barber’s Itch) — Merck Manual Professional Edition. 2024. https://www.merckmanuals.com/professional/dermatologic-disorders/fungal-skin-infections/tinea-barbae-barber-s-itch
- Tinea Barbae (ringworm of the beard) — Yale Medicine. 2023. https://www.yalemedicine.org/clinical-keywords/tinea-barbae
- Tinea Barbae (Ringworm on Beard) — Skinsight. 2023. https://skinsight.com/skin-conditions/tinea-barbae-ringworm-of-beard/



