
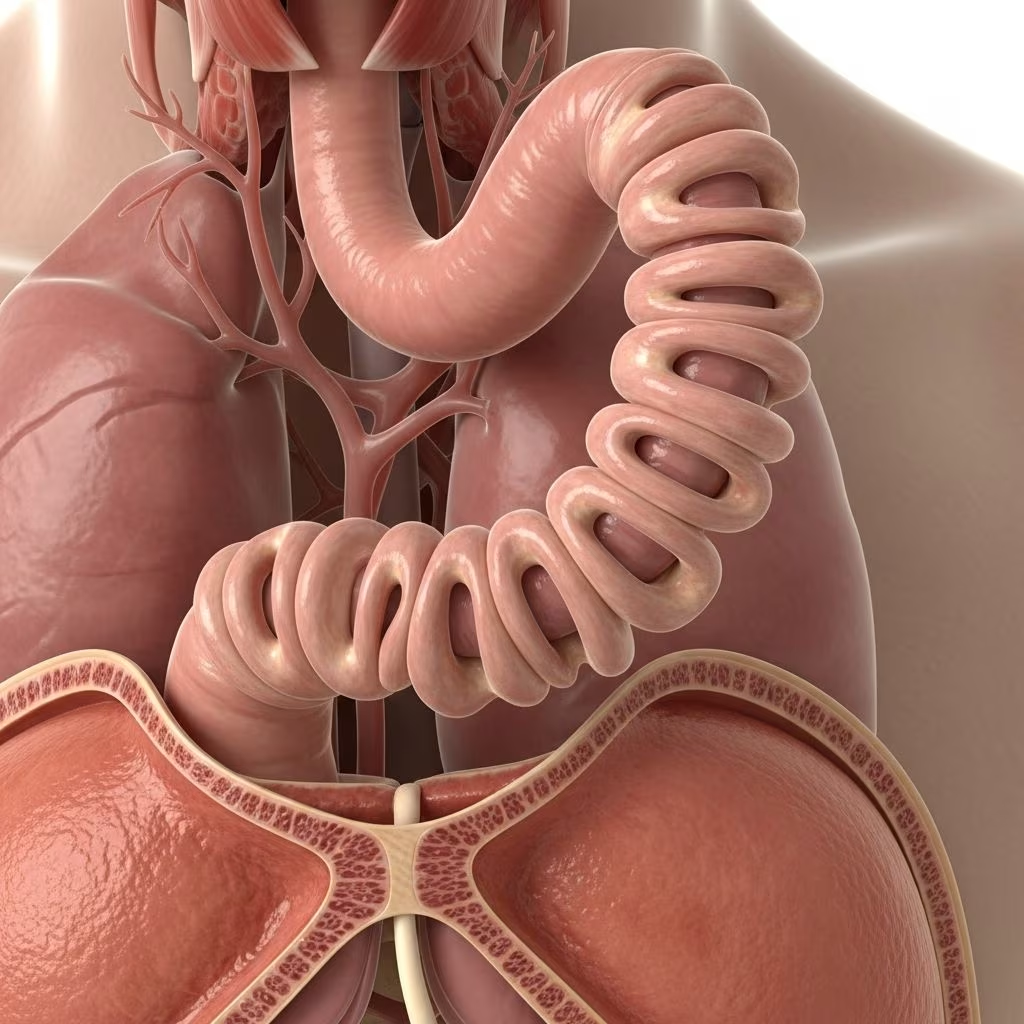
Corkscrew esophagus, also known as diffuse esophageal spasm (DES), is a rare esophageal motility disorder characterized by simultaneous, uncoordinated contractions of the esophagus that give it a twisted, corkscrew appearance on imaging.
What Is Corkscrew Esophagus?
Corkscrew esophagus belongs to a group of primary esophageal motility disorders, which disrupt the normal wave-like peristalsis that propels food from the mouth to the stomach. In this condition, the esophagus exhibits simultaneous contractions rather than sequential peristalsis, leading to a characteristic spiraling pattern visible on barium swallow studies or endoscopy. These spasms can occur in the esophageal body, often sparing the lower esophageal sphincter in some cases, though impaired relaxation may also be present.
The disorder is uncommon, affecting a small subset of patients with swallowing complaints. It differs from related conditions like nutcracker esophagus (hypertensive peristalsis) and achalasia (hypertensive lower esophageal sphincter with absent peristalsis). In DES, manometry typically shows high-amplitude, non-peristaltic contractions in over 20% of swallows, confirming the diagnosis.
Symptoms of Corkscrew Esophagus
Patients with corkscrew esophagus often experience intermittent symptoms that mimic other gastrointestinal or cardiac issues. Common manifestations include:
- Dysphagia: Difficulty swallowing solids and liquids, with food feeling ‘stuck’ in the chest. This can worsen gradually over weeks to months.
- Chest pain: Retrosternal burning, tightness, or severe pain unrelated to meals or exertion, sometimes triggered by anxiety or hiccups.
- Regurgitation: Undigested food returning to the mouth without sour taste or bile, often requiring upright positioning to swallow.
- Acid reflux-like symptoms: Heartburn or odynophagia (painful swallowing), though true GERD may coexist or be absent.
Symptoms are episodic, lasting minutes to hours, and can be provoked by cold liquids, stress, or rapid eating. In one case, a 51-year-old woman reported 4-year history of retrosternal burning and chest tightness without significant dysphagia, exacerbated by anxiety. Another 80-year-old patient described 4 weeks of progressive dysphagia for solids and liquids with regurgitation.
Causes and Risk Factors
The exact cause of corkscrew esophagus remains unclear, but it involves dysfunctional esophageal smooth muscle coordination. Potential contributors include:
- Neuromuscular abnormalities: Impaired inhibitory innervation leading to unopposed cholinergic stimulation and spasm.
- Associated conditions: Links to rheumatoid arthritis (RA), anxiety disorders, thoracic aortic aneurysm, atrial fibrillation, or COPD, as seen in comorbid patients.
- Triggers: Emotional stress, hot/cold foods, or medications affecting esophageal motility.
No strong genetic or familial predisposition is established, though cases report no family history. It is classified as a primary motility disorder, distinct from secondary spasms due to scleroderma or diabetes.
Diagnosis of Corkscrew Esophagus
Diagnosis requires a combination of clinical history, imaging, and functional tests to rule out mimics like achalasia, GERD, or cardiac disease. Key diagnostic steps include:
- Barium esophagogram: Reveals ‘corkscrew’ or tertiary contractions—simultaneous, non-propulsive waves giving a spiral appearance.
- Upper endoscopy: Shows winding, staircase-like distal esophagus; rules out strictures or malignancy.
- Esophageal manometry: Gold standard—demonstrates absent peristalsis, simultaneous contractions (>20% of swallows), and sometimes impaired LES relaxation.
In a reported case, barium study showed abnormal spiral peristalsis, endoscopy confirmed distal corkscrew look, and manometry verified alternative peristalsis patterns. Physical exam is often normal, though comorbidities like RA deformities may be evident.
Treatment Options for Corkscrew Esophagus
No standardized guidelines exist; management is symptom-driven and individualized. Initial approaches focus on lifestyle and pharmacotherapy, escalating to invasive options if needed.
Lifestyle Modifications
- Eat slowly, chew thoroughly, and avoid extreme temperatures in food/drink.
- Stay upright after meals; small, frequent meals reduce spasm risk.
- Manage stress through relaxation techniques.
Medications
Pharmacologic agents relax smooth muscle or reduce contraction amplitude:
| Drug Class | Examples | Mechanism | Efficacy Notes |
|---|---|---|---|
| Calcium Channel Blockers (CCBs) | Nifedipine, Diltiazem | Inhibit calcium influx, reducing contraction strength | Diltiazem 90 mg SR q12h improved symptoms in one case |
| Nitrates | Sublingual nitroglycerin, Isosorbide dinitrate | Promote smooth muscle relaxation | Taken before meals for acute relief |
| Antidepressants | Trazodone (low-dose), Imipramine | Modulate visceral pain and motility | Effective in trials for noncardiac chest pain |
| Other | Sildenafil (PDE inhibitor), Bethanechol | Improve bolus transit; investigational | Preliminary benefits in studies |
Antireflux therapy (PPIs) may help if GERD overlaps, though one patient saw no relief after 6 months. Diltiazem provided significant improvement in an elderly patient.
Advanced Therapies
- Botulinum toxin injection: Into gastroesophageal junction for refractory spasm; supported by small trials.
- Endoscopic or surgical interventions: Myotomy (Heller) for severe cases unresponsive to meds.
Complications and Prognosis
Untreated DES can lead to weight loss from dysphagia, aspiration risk, or malnutrition. Most patients achieve symptom control with conservative measures. Long-term prognosis is good, with spasms not progressing to achalasia. Regular follow-up monitors comorbidities like RA or aneurysms.
When to See a Doctor
Seek immediate care for new/worsening dysphagia, unexplained chest pain (rule out heart disease), or regurgitation. Gastroenterologist referral is essential for motility testing.
Frequently Asked Questions (FAQs)
What causes the corkscrew appearance in the esophagus?
Simultaneous, high-amplitude contractions replace normal peristalsis, creating a twisted pattern on barium studies or endoscopy.
Is corkscrew esophagus the same as achalasia?
No; achalasia features absent peristalsis and LES hypertension, while DES has spasms with variable LES function.
Can corkscrew esophagus cause heartburn?
Yes, spasms mimic reflux, but endoscopy distinguishes it from true GERD.
How is diffuse esophageal spasm treated?
With CCBs like diltiazem, nitrates, or antidepressants; botox for refractory cases.
Is surgery needed for corkscrew esophagus?
Rarely; reserved for medication failures after optimizing conservative therapy.
Living with Corkscrew Esophagus
Patients can manage symptoms effectively by modifying diet (soft foods, avoid triggers), adhering to medications, and addressing psychological factors like anxiety. Support from gastroenterologists ensures tailored care, improving quality of life. Ongoing research refines treatments, but current options provide relief for most.
References
- Corkscrew esophagus — F. Lin et al. QJM: An International Journal of Medicine. 2017-02-28. https://academic.oup.com/qjmed/article/doi/10.1093/qjmed/hcx026/2993113
- Corkscrew Esophagus — Mrugesh Patel, MD, Mario J. Madruga, MD. Consultant360. 2011-08-01. https://www.consultant360.com/content/corkscrew-esophagus



